
Published | Last updated
Mendelian randomization (MR) uses the genetic variants a person inherits at conception as natural instruments to test whether a modifiable exposure actually causes a disease outcome, rather than simply moving alongside it in cohort data. Editverse has supported more than 1,100 manuscripts, and the single objection our statisticians see most often on an observational causal claim is some version of “the authors have not ruled out confounding or reverse causation.” Mendelian randomization is the design that answers that objection most directly, and it has moved from a specialist genetic-epidemiology technique into a routine expectation across cardiology, nutrition, psychiatry, nephrology, and oncology journals over the past decade.
What follows works through the genetic logic that makes the method credible, the three instrumental-variable assumptions a statistical reviewer checks first, the estimators used in current two-sample and multivariable designs, pleiotropy as the assumption most likely to fail in practice, and three published examples spanning cardiovascular, nutritional, and behavioral epidemiology. Every study referenced below carries its PubMed identifier or DOI so you can read the original finding rather than take a summary on faith.
In Simple Words
Because which genetic variant you inherit is decided randomly when your parents’ chromosomes recombine, that variant splits a population into two groups the way a coin flip would, one nudged toward higher lifelong exposure to something like LDL cholesterol or alcohol intake, one not. Neither group chose its genotype, and neither group’s genotype was shaped by diet, income, or a habit picked up later in life. So if disease rates differ between the two groups, and the variant changes nothing else besides that one exposure, the difference is evidence the exposure itself moves disease risk, not just evidence the two things happen to travel together.
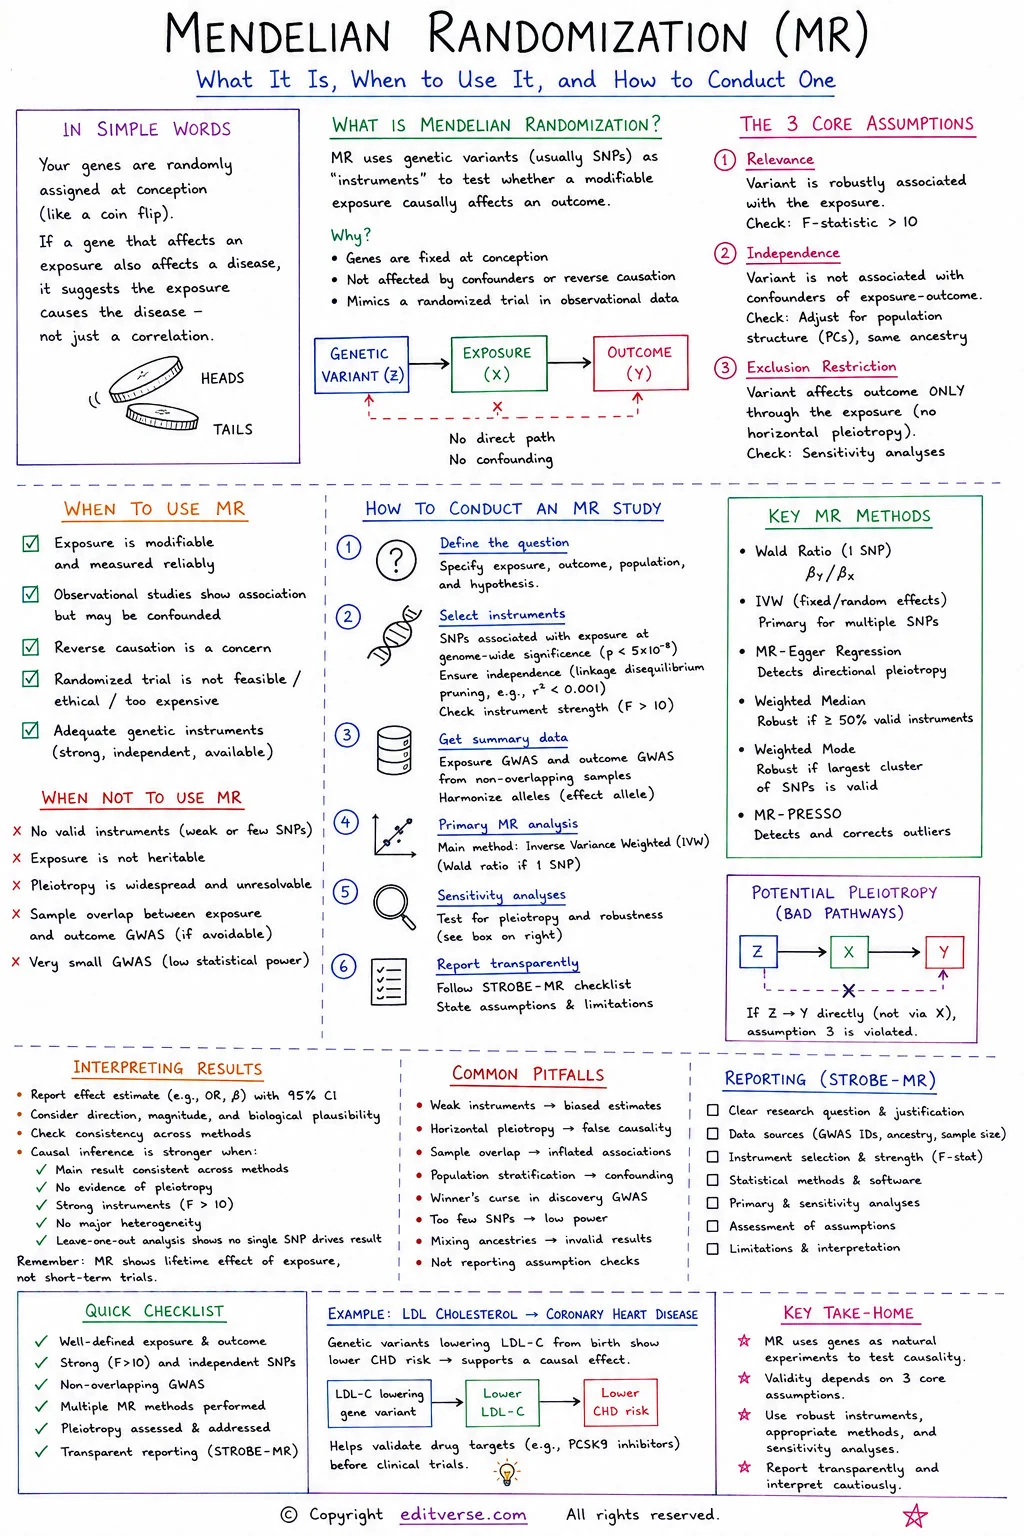
What Is Mendelian Randomization?

Genotype is fixed at conception, so it sits upstream of the diet, behavior, and social circumstances that confound an ordinary observational comparison. That timing is what lets a genetic variant stand in for random allocation (Sanderson et al., 2022). George Davey Smith and Shah Ebrahim popularized the term in a 2003 paper that framed germline genetic variation as a natural experiment already running in every cohort study ever collected, no recruitment or follow-up required (Davey Smith and Ebrahim, 2003). Two decades of genome-wide association studies have since produced summary statistics for thousands of exposures and outcomes, turning the design from a theoretical proposal into one of the most frequently applied causal-inference tools in epidemiology.
Mendelian randomization is an application of instrumental variable analysis in which a genetic variant, usually a single nucleotide polymorphism or a weighted combination of several, proxies a modifiable exposure. That logic rests on Mendel’s law of independent assortment, since alleles are distributed to offspring at random during meiosis, so a person’s genotype at a given locus is set before birth and cannot be altered by the smoking, socioeconomic status, or disease progression that plague conventional cohort comparisons (Sekula et al., 2016; Sanderson et al., 2022).
Every analysis is built from three linked pieces.
- The instrument. One or more genetic variants robustly associated with the exposure.
- The exposure. The modifiable risk factor under study, for example LDL cholesterol, body mass index, C-reactive protein, or alcohol intake.
- The outcome. The disease or trait of interest, for example coronary artery disease, type 2 diabetes, or depression.
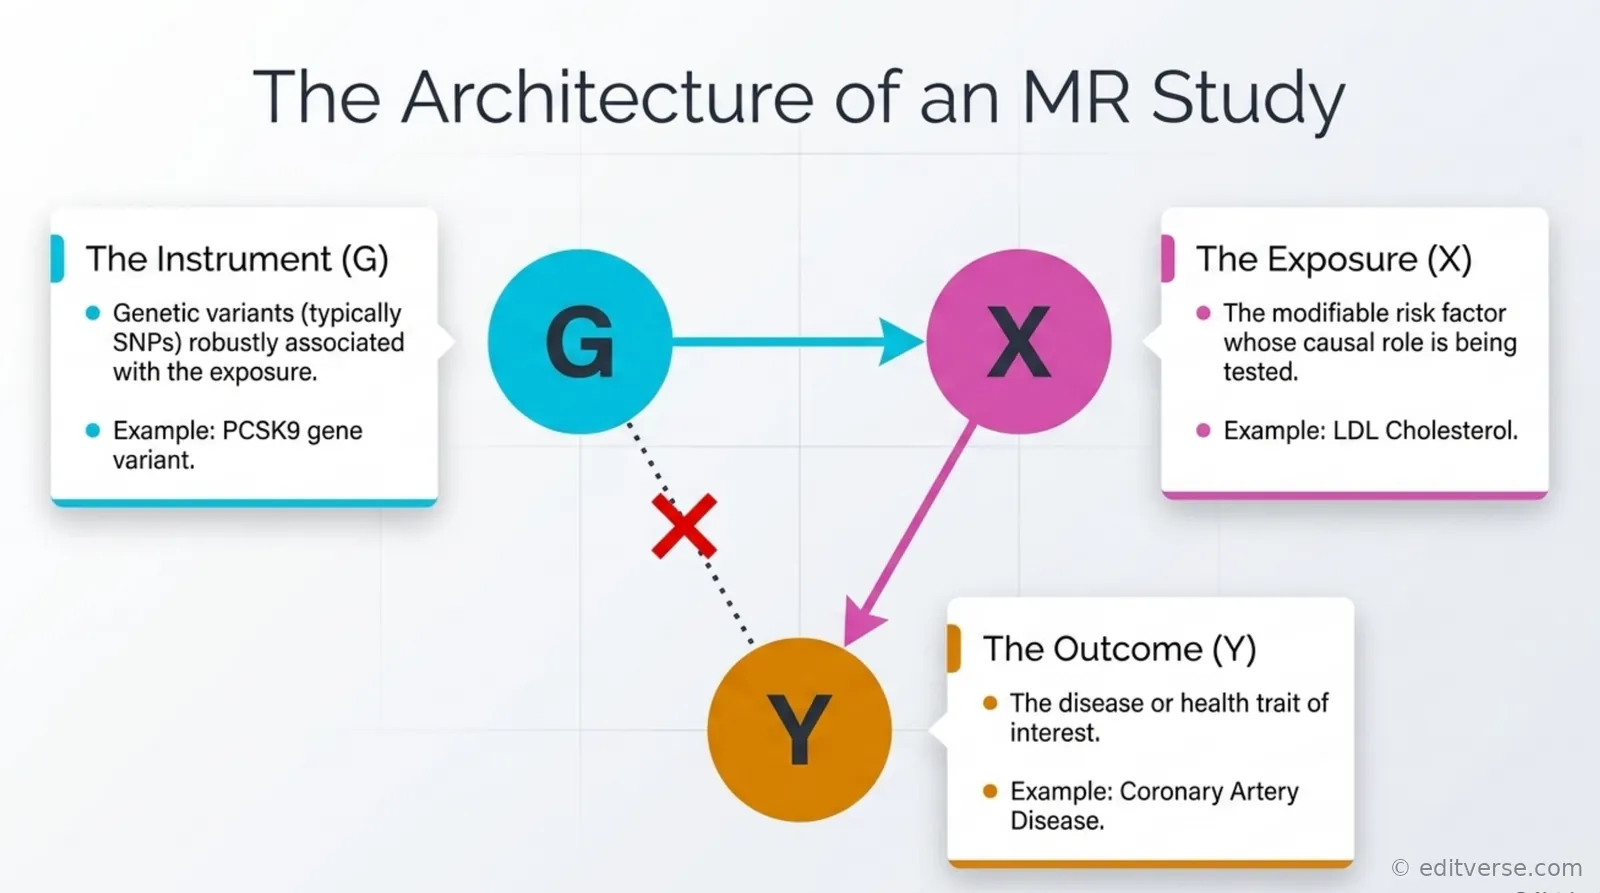
Reviewers at journals such as JAMA and the European Heart Journal now expect a manuscript to name each of the three components explicitly and to justify the instrument choice with a citation to the source GWAS, not simply to assert that “genetic variants were used as instruments.”
The Three Core Assumptions Behind Every Mendelian Randomization Study
A causal estimate from this design is only as trustworthy as three instrumental-variable assumptions, and STROBE-MR item 5 requires authors to state explicitly how each one was assessed (Skrivankova et al., 2021).

Relevance. A valid instrument needs a strong, well-powered association with the exposure it proxies. Practice checks this with the F-statistic from the variant-exposure regression. Burgess and Thompson showed that an F-statistic below 10 signals a weak instrument that biases the causal estimate toward the confounded observational association rather than away from it, and the bias grows worse as sample overlap between exposure and outcome data increases (Burgess and Thompson, 2011).
Independence, also called exchangeability. No confounder of the exposure-outcome relationship should associate with the variant either. Nobody can test this assumption directly. Restricting the sample to one ancestry group and adjusting for genetic principal components makes it more plausible by ruling out population stratification, a confound that arises when allele frequencies and disease rates both vary by ancestry for reasons unrelated to biology.
Exclusion restriction. A valid variant changes the outcome only through the exposure being studied, never through an independent biological pathway. Violations here are the most common failure mode in practice. A gene that influences body weight through appetite regulation and also independently affects inflammation would break exclusion restriction for a body-weight-and-cardiovascular-disease analysis, because part of its effect on the outcome would bypass the exposure entirely. That failure mode, horizontal pleiotropy, is common enough that a dedicated toolkit of sensitivity analyses now exists to probe it, covered later in this guide.
Common MR Study Designs and Estimators
Two structural choices and a family of statistical estimators define current practice. Getting either wrong is one of the fastest ways to draw a reviewer’s major-revision request.
One-sample MR draws genotype, exposure, and outcome from the same cohort, commonly UK Biobank. One-sample designs support non-linear dose-response modeling and let you check instrument strength directly in your target population, but they require access to individual-level genotype data and a large enough cohort to power the analysis.
Two-sample MR is now the dominant approach, combining summary statistics from two non-overlapping genome-wide association studies, one that estimated the variant-exposure association and one that estimated the variant-outcome association (Burgess, Butterworth, and Thompson, 2013). Because it needs only published summary data rather than raw genotypes, two-sample MR opened the method to researchers without a genotyped cohort of their own, which is the single biggest reason its use has expanded so quickly outside specialist genetics groups. Sample overlap between the two GWAS remains a real hazard even here, discussed under common mistakes below.
Once the design is fixed, several estimators are typically run side by side rather than in isolation.
- Inverse-variance weighted (IVW) regression is the standard primary estimator for two-sample MR with multiple instruments. It regresses SNP-outcome estimates on SNP-exposure estimates, weighting each variant by the inverse of its variance, and assumes every instrument is valid (Burgess, Butterworth, and Thompson, 2013).
- MR-Egger regression adds an intercept term that is allowed to differ from zero, which detects and adjusts for directional pleiotropy at the cost of wider confidence intervals and lower statistical power (Bowden, Davey Smith, and Burgess, 2015).
- The weighted median estimator stays consistent even when up to half the instrument weight comes from invalid variants, which makes it a useful check against a single dominant pleiotropic SNP distorting the IVW result (Bowden, Davey Smith, Haycock, and Burgess, 2016).
- Multivariable MR extends the framework to two or more exposures simultaneously, estimating the direct effect of each while holding the others constant. It is the tool of choice when exposures are genetically correlated, for example LDL cholesterol and apolipoprotein B, and it doubles as a Mendelian randomization approach to mediation analysis, quantifying how much of a total genetic effect on an outcome runs through a specified intermediate exposure (Sanderson, 2021).
No single estimator is safe to report alone. Current guidance recommends triangulating several and checking that the direction and rough magnitude of the causal estimate hold up across methods with different bias structures (Burgess et al., 2023). Agreement between them is necessary but not sufficient, and our simulation of what each of the four estimators actually protects you from sets out which assumption each one relaxes, and the regime in which all four agree on the same wrong answer.
Pleiotropy, the Central Threat to Validity
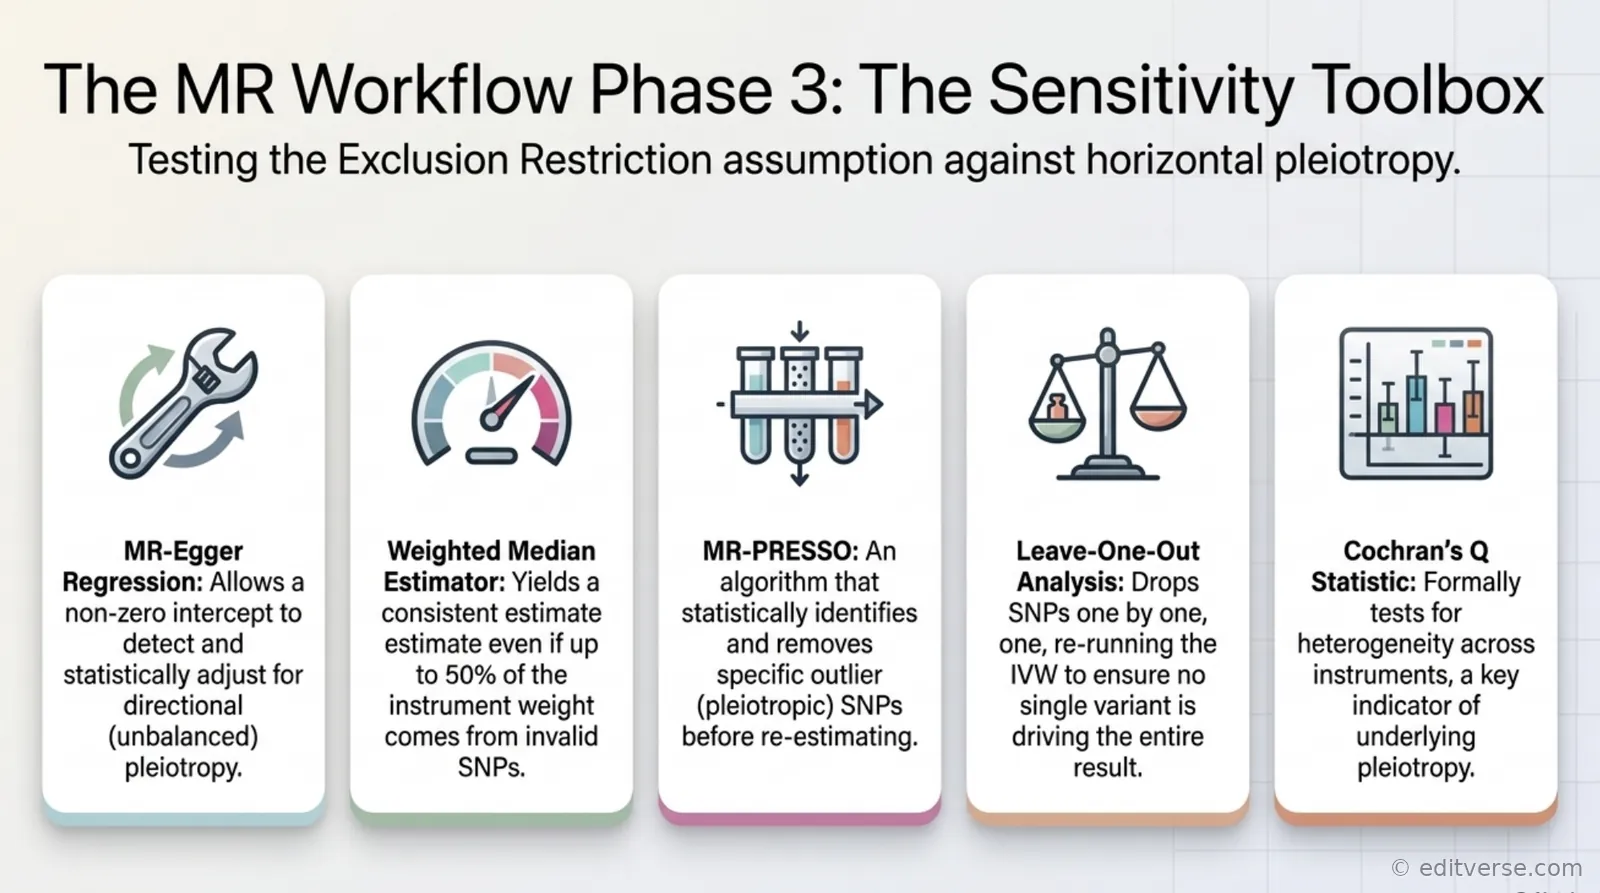
Vertical pleiotropy, where a variant affects the outcome only by first changing the exposure, is harmless and expected. Horizontal pleiotropy, where a variant reaches the outcome through a second pathway that bypasses the exposure, is what breaks exclusion restriction and biases the causal estimate. Verbanck and colleagues built the MR-PRESSO test specifically to flag horizontal pleiotropic outlier variants in multi-instrument summary-data analyses, then applied it across a wide set of published exposure-outcome pairs. Those results were striking. Horizontal pleiotropy was detectable in over 48% of significant causal relationships, it distorted causal estimates by an average of -131% to 201%, and it produced false-positive causal claims in up to 10% of the relationships tested (Verbanck et al., 2018). That single study is why a methods section reporting only an IVW estimate, with no pleiotropy check attached, now draws an almost automatic reviewer objection.
A defensible analysis runs several checks together rather than trusting any one of them alone.
- MR-PRESSO statistically identifies and removes outlier SNPs likely to be pleiotropic, then re-estimates the effect without them (Verbanck et al., 2018).
- Leave-one-out analysis reruns the IVW estimate while dropping one variant at a time, confirming that no single SNP is driving the whole result.
- Cochran’s Q statistic formally tests for heterogeneity across instruments, which often signals pleiotropy even when no individual variant looks like an outlier.
- MR-Egger’s intercept test gives a direct, if low-powered, test for directional pleiotropy across the full instrument set (Bowden, Davey Smith, and Burgess, 2015).
Three Worked Examples From Recent Mendelian Randomization Literature
LDL Cholesterol and Coronary Heart Disease
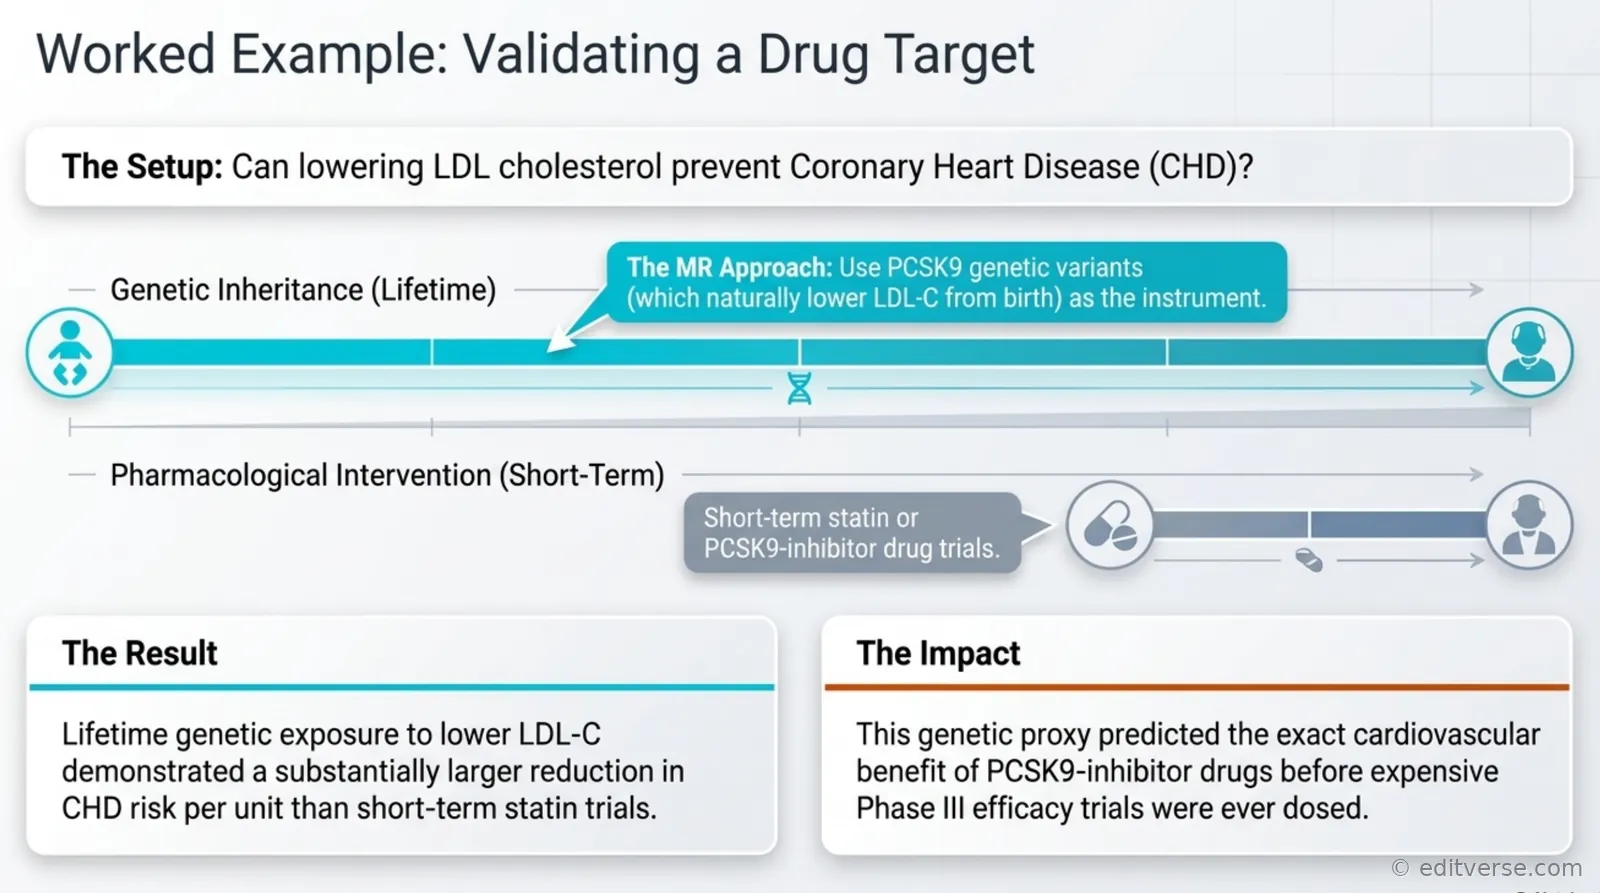
Ference and colleagues used variants that lower LDL cholesterol from birth as a proxy for lifetime, rather than short-term, exposure, then estimated the effect of long-term LDL-C reduction on coronary heart disease risk. Lifetime genetic exposure to lower LDL-C tracked with a substantially larger reduction in coronary heart disease risk per unit of LDL-C lowering than the same absolute reduction achieved over the few years of a statin trial, a pattern consistent with a cumulative, duration-dependent effect that a short randomized trial is not positioned to capture on its own (Ference et al., 2012).
That same logic now validates drug targets before a Phase III trial gets funded. Gagnon and colleagues genotyped and RNA-sequenced 504 human liver samples to build two genetic proxies for two different PCSK9-lowering drug mechanisms, a variant explaining 5.6% of liver PCSK9 expression to mimic RNA-interference therapy and the PCSK9 R46L functional variant to mimic antibody-based inhibition. For each standard-deviation decrease in apolipoprotein B, the two mechanistically different variants were associated with closely comparable reductions in coronary artery disease risk, predicting that RNA-interference and antibody-based PCSK9 inhibitors should deliver similar cardiovascular benefit per unit of lipid lowering before a single head-to-head outcomes trial reported (Gagnon et al., 2025). Drug-target Mendelian randomization of this kind is now standard practice at several major pharmaceutical companies, because it is faster and cheaper than an early-phase efficacy trial while still resting on a randomized, genetic allocation mechanism.
Vitamin D and Multiple Health Outcomes
Vitamin D is a useful worked example because observational cohorts have linked low levels to an implausibly long list of conditions, a pattern that is a textbook signature of confounding by outdoor activity, diet quality, and body fat rather than a single unifying biology. Fang and colleagues systematically reviewed the Mendelian randomization literature on vitamin D published through September 2022, pooling 133 separate MR publications that together examined 275 individual outcomes. Genetically predicted 25-hydroxyvitamin D held up as protective for a specific, biologically coherent subset of that list, including multiple sclerosis incidence and relapse, non-infectious uveitis and scleritis, psoriasis, and fracture risk at the femur and leg (Fang et al., 2024). Zhao and colleagues then tested the same exposure specifically against autoimmune and autoinflammatory disease in 332,984 UK Biobank participants, of whom 23,089 carried at least one qualifying diagnosis, and found genetically predicted vitamin D associated with lower risk within the autoinflammatory disease subgroup (Zhao et al., 2023). Read together, the two studies show why an outcome-wide genetic screen earns its place alongside a single cohort correlation. It keeps the specific associations with a defensible biological mechanism and lets the much longer list of correlations that observational data alone could not explain fall away.
Alcohol Consumption and Disease Risk Through ALDH2
Alcohol epidemiology has a confounding problem that is unusually hard to solve by adjustment alone, because people who drink heavily also tend to smoke more, exercise less, and eat differently, and light drinkers are sometimes former heavy drinkers who cut back for health reasons already in progress. East Asian populations offer a natural genetic instrument for this exact problem. A common variant in ALDH2 (rs671) impairs acetaldehyde metabolism, so carriers experience facial flushing and nausea after drinking and consume substantially less alcohol on average than non-carriers, essentially independent of the social and behavioral factors that confound self-reported drinking. Millwood and colleagues used this variant, together with a related ADH1B polymorphism, as genetic instruments in a prospective study of 500,000 men and women across ten areas of China. Genetic evidence confirmed that alcohol increases stroke risk, matching the conventional observational association, but it also overturned the popular claim of a cardioprotective effect from moderate drinking. Apparent protection seen in observational data did not hold up against the genetic instrument, indicating it was very likely an artifact of confounding rather than a genuine biological effect of moderate alcohol intake (Millwood et al., 2019).
When Should You Use Mendelian Randomization?

Mendelian randomization earns its place in a study design under a handful of recurring conditions.
A randomized controlled trial is not feasible or ethical
Nobody can randomize people to smoke, gain weight, or carry high LDL cholesterol for thirty years to observe the cardiovascular consequences. A genetic instrument approximates that impossible trial using variation that was already randomized at conception (Larsson, Butterworth, and Burgess, 2023).
Reverse causation is a plausible alternative explanation
Depression and inflammation, or kidney function and blood pressure, can each plausibly cause the other. Genotype is fixed from birth, so it cannot be caused by a disease that develops decades later, which severs the reverse-causation pathway that undermines cross-sectional and even longitudinal cohort designs.
Residual and unmeasured confounding is a real concern
Multivariable regression can adjust only for confounders that were actually measured, and diet, socioeconomic status, and health-seeking behavior are notoriously incomplete in most cohorts. A genetic instrument is independent of these factors by design, provided the independence assumption holds, which makes the method considerably less vulnerable to residual confounding than propensity score matching or multivariable adjustment applied to the same observational data. That contrast matters in practice: a nationally representative survey analysis can be weighted and adjusted correctly and still leave the exposure-outcome association open to confounding, as our walkthrough of what NHANES survey weights do and do not fix shows on real data. Our companion guide on propensity score matching covers the complementary approach of balancing measured covariates rather than removing their influence by genetic design.
A drug target needs triangulation or validation
Because a variant that lowers a biomarker such as PCSK9 or IL-6R mimics the pharmacological action of a drug targeting the same pathway, drug-target Mendelian randomization is now routine in early development to predict whether a compound is likely to show clinical benefit, and to flag on-target side effects, before a costly Phase III trial begins (Larsson, Butterworth, and Burgess, 2023).
Large-scale GWAS summary statistics already exist
Two-sample designs depend on adequately powered GWAS for both the exposure and the outcome, ideally drawn from non-overlapping samples in the tens of thousands to hundreds of thousands of participants. Where no GWAS of adequate size exists for the exposure of interest, the method is usually not yet a workable option.
When not to reach for it. Skip Mendelian randomization if a well-conducted randomized trial already answers the causal question, if no genetic instrument exists for the exposure, if the available genotyped sample runs to only a few thousand people, or if the exposure is not a discrete, biologically well-characterized trait, such as a bundled policy intervention with no single genetic proxy.
How to Conduct a Mendelian Randomization Study

Formulate a precise causal question and check feasibility. State the exposure and outcome explicitly, for example “does genetically predicted higher body mass index cause knee osteoarthritis.” Confirm a GWAS of adequate size exists for the exposure and reports full summary statistics, or is queryable through a repository such as IEU OpenGWAS, FinnGen, or the GWAS Catalog.
Choose one-sample or two-sample design using the tradeoffs described above, then select genetic instruments by extracting SNPs that reach genome-wide significance, typically p < 5 × 10⁻⁸, for the exposure GWAS. Clump variants by linkage disequilibrium, commonly r² < 0.001 within a 10,000 kb window, so only independent signals remain, and calculate the F-statistic for each instrument or the mean F across the full set, flagging anything below 10.
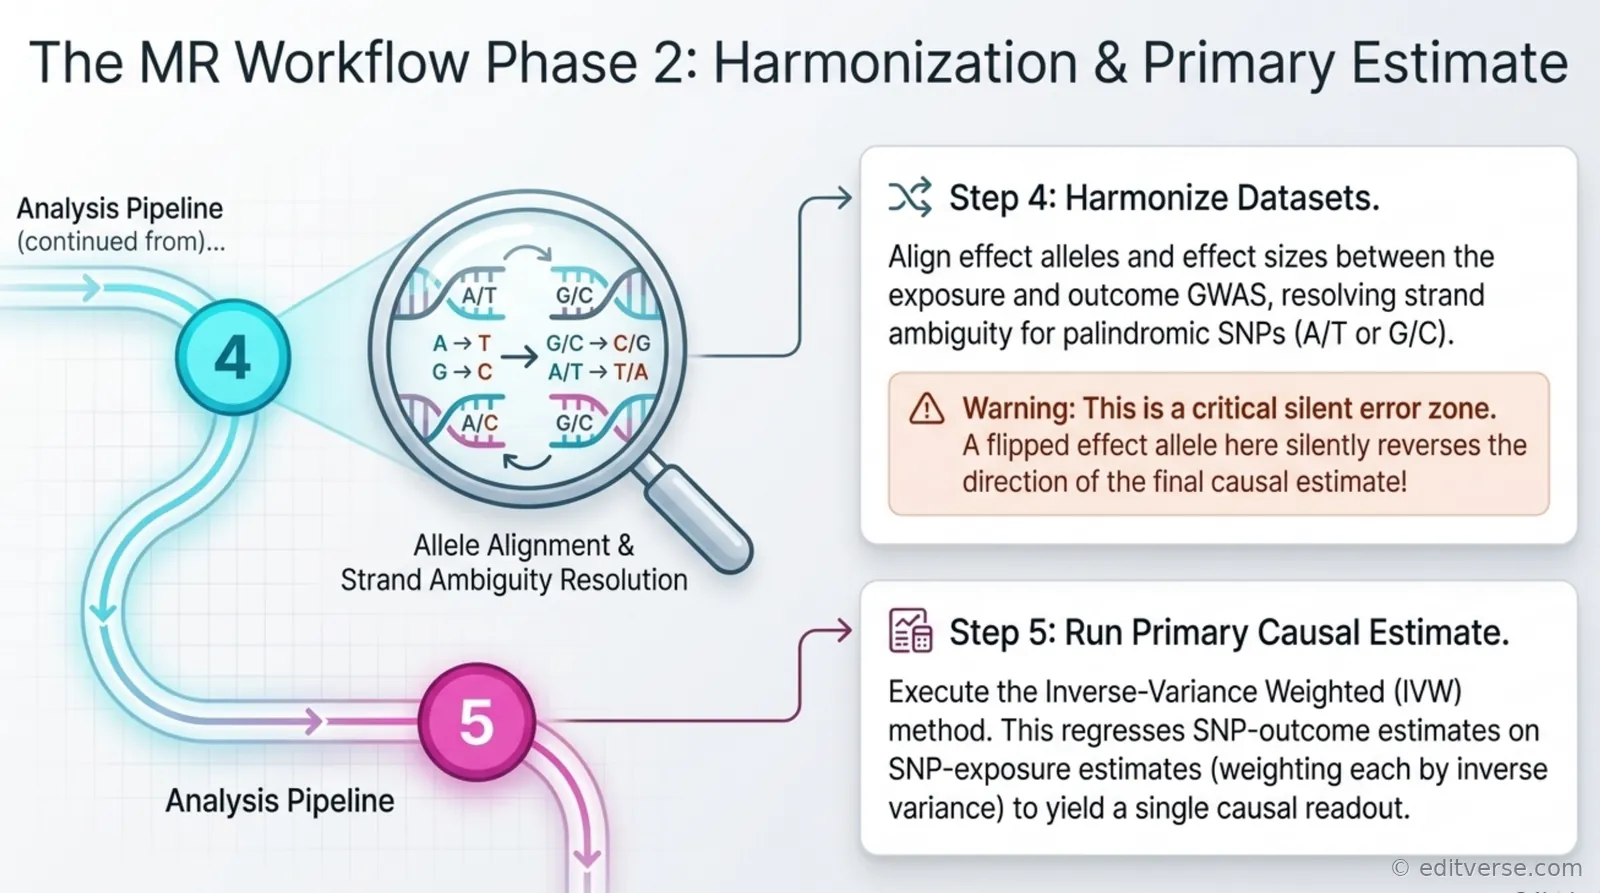
Harmonize the exposure and outcome datasets by aligning effect alleles and effect sizes, resolving strand ambiguity for palindromic SNPs whose alleles read A/T or G/C on either strand, and dropping variants that cannot be confidently matched. That step is mechanical, and it is also where silent errors creep in most often. A flipped effect allele quietly reverses the direction of a causal estimate without producing any error message.
Run the primary causal estimate with inverse-variance weighting, then run the sensitivity battery described in the pleiotropy section above rather than stopping at IVW alone.

Report according to STROBE-MR. STROBE-MR lays out a 20-item checklist that requires authors to justify their instrument choice, report the F-statistic, disclose every sensitivity analysis run rather than only the flattering ones, and state plainly which of the three instrumental-variable assumptions could not be empirically verified (Skrivankova et al., 2021). That checklist extends the general reporting logic covered in our STROBE guidelines tutorial, and several journals now require the completed version as a supplementary file at initial submission.
Data Sources and Software for MR Analysis
| Resource | Type | Typical Use |
|---|---|---|
| IEU OpenGWAS (MRC IEU, Bristol) | GWAS summary statistics database | Source of exposure and outcome GWAS for two-sample designs |
| FinnGen | National biobank GWAS | Disease-outcome GWAS in a Finnish founder population |
| UK Biobank | Individual-level cohort, about 500,000 participants | One-sample MR, non-linear dose-response modeling |
| NHGRI-EBI GWAS Catalog | Curated variant-trait associations | Instrument identification and cross-checking |
TwoSampleMR (R package) | Analysis software | Harmonization, IVW, MR-Egger, weighted median |
MendelianRandomization (R package) | Analysis software | Alternative implementation of the core estimators |
MR-PRESSO (R package) | Pleiotropy detection | Outlier SNP identification and correction |
Common Mistakes in Mendelian Randomization to Avoid

Across the manuscripts our statisticians review, a small set of errors accounts for most of the revision requests and desk rejections tied to this method.
- Using a weak instrument without reporting the F-statistic. Reviewers routinely ask for this in the first round, and omitting it is one of the fastest routes to a major revision (Burgess and Thompson, 2011).
- Reporting only the IVW estimate. A single method cannot distinguish a genuine causal effect from one driven by pleiotropy. Editors increasingly expect MR-Egger and the weighted median alongside IVW as a minimum.
- Ignoring sample overlap in two-sample designs. When the exposure and outcome GWAS partially share participants, standard errors are underestimated and false positives become more likely, an effect Burgess, Davies, and Thompson quantified directly by simulation (Burgess, Davies, and Thompson, 2016).
- Mixing ancestries without adjustment. Combining GWAS from different ancestral populations without accounting for population stratification can introduce confounding through allele-frequency differences alone, with no biological cause at all.
- Overinterpreting a null result as proof of no causal effect. A null estimate with wide confidence intervals more often reflects low statistical power than a genuinely absent effect, and that distinction needs to be stated explicitly rather than implied.
- Skipping the STROBE-MR checklist at submission. Several journals now require it as a supplementary file, and its absence is an easy first-round rejection trigger during an editorial completeness check, well before a paper reaches peer review.
Mendelian Randomization vs. Other Causal Inference Methods
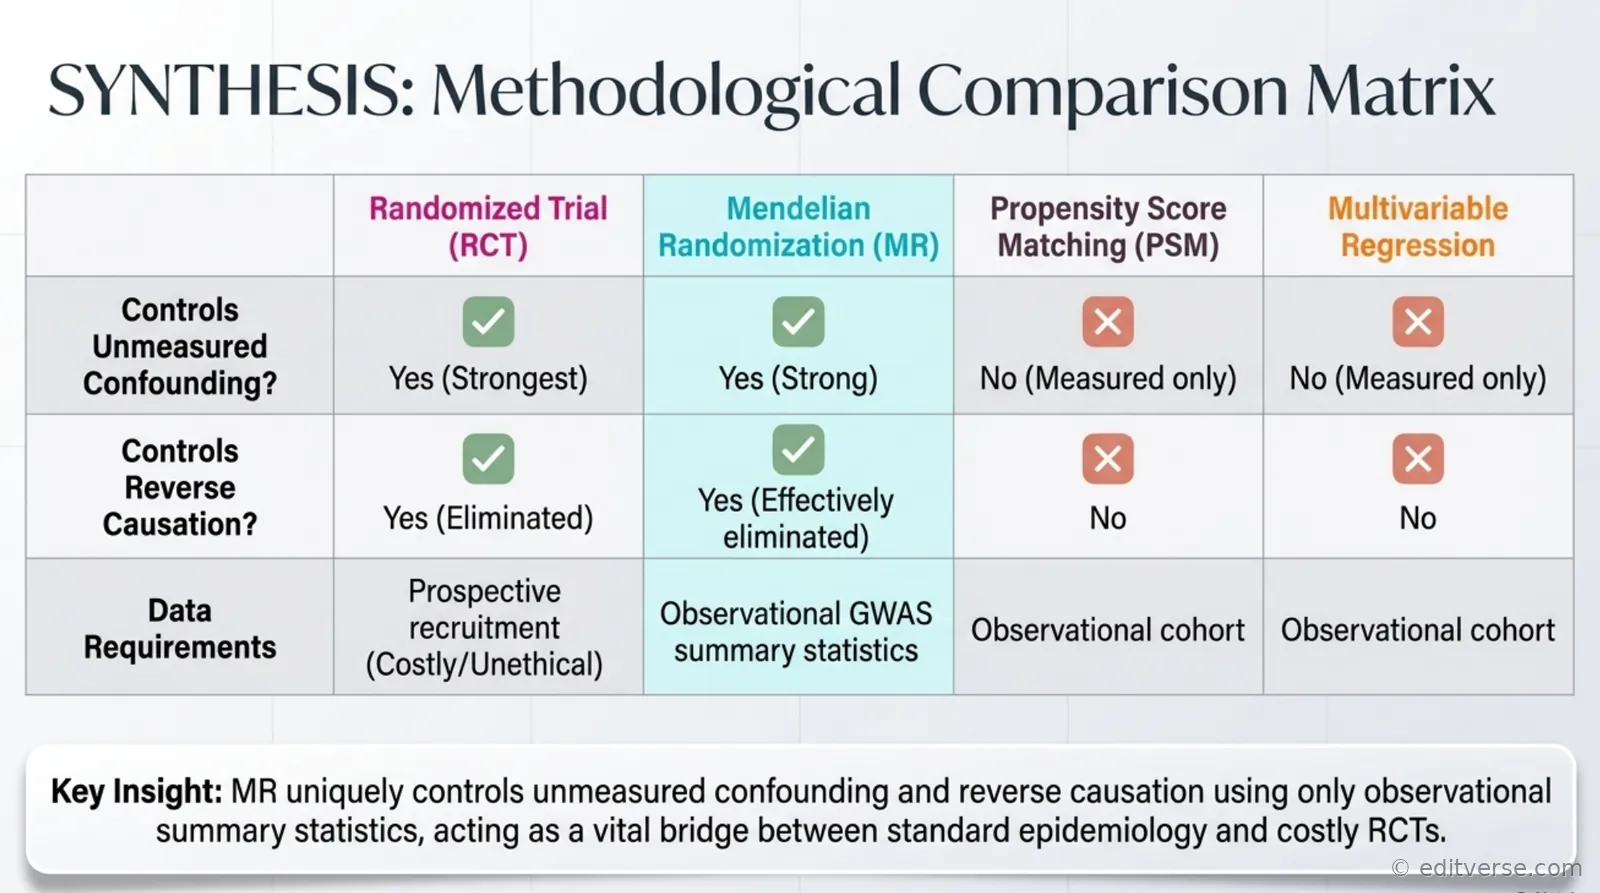
| Method | Confounding Control | Reverse Causation | Data Requirement |
|---|---|---|---|
| Randomized controlled trial | Strongest, by design | Eliminated | Prospective recruitment, often costly or unethical |
| Mendelian randomization | Strong for unmeasured confounding | Effectively eliminated | GWAS summary statistics for exposure and outcome |
| Propensity score matching | Only for measured confounders | Not addressed | Observational cohort with covariates |
| Multivariable regression | Only for measured confounders | Not addressed | Observational cohort with covariates |
Rather than competing, the four designs complement each other, since each carries a different bias structure. Agreement across a genetic instrument, a matched comparison, and an adjusted regression, a strategy called triangulation, is far more persuasive than any single method taken alone (Lawlor, Tilling, and Davey Smith, 2016). Many strong manuscripts now report a conventional adjusted or matched analysis alongside a genetic sensitivity check for exactly this reason. For background on instrumental variable methods outside genetics, on the broader logic of causal inference in epidemiology, and on the GWAS data layer this method depends on, see our primer on GWAS statistical methods. Where the causal question involves an intermediate step rather than a single exposure, our guide to mediation analysis covers the non-genetic version of the same decomposition that multivariable MR performs with genetic instruments. And where the outcome comes from a randomized trial rather than a cohort, the RCT design and analysis guide and our intention-to-treat versus per-protocol guide cover the population-definition choices that determine what that trial estimate actually means.
Professional Support for a Mendelian Randomization Study
The methodological bar described above is now the working editorial standard, and it is also the reason so many submitted MR papers are returned without review. The core estimate is rarely the problem. What fails is the missing half of the analysis: no F-statistics, no Steiger filtering, no instrument PheWAS, a single estimator reported as though the pleiotropy question had never been raised. Our biostatisticians run the full battery in R using TwoSampleMR, MendelianRandomization and MR-PRESSO, and deliver the analysis with a completed STROBE-MR checklist rather than leaving the reporting to you.
Feasibility Check
$450
Instrument count, F-statistics, sample overlap and existing literature checked before you commit. Go, modify or stop, in writing. Credited in full against any study you then commission. 5 business days.
Two-Sample MR
$2,900
Full study from public GWAS summary statistics: four estimators, MR-PRESSO, Steiger filtering, instrument PheWAS, leave-one-out, plus a completed STROBE-MR checklist and runnable R code. 15 business days.
Extended Designs
From $3,500
Multivariable MR for correlated exposures, mediation MR, colocalisation, drug-target MR and non-linear MR. Fixed quote and written scope before any work begins.
If you are still deciding whether a genetic design is the right one, or weighing it against a survey, cancer registry or trauma registry analysis, start with our guide to which health database your study should use. For statistical support on a design outside this category, our dissertation statistical analysis service covers the broader modelling work.
Frequently Asked Questions About Mendelian Randomization
Is Mendelian randomization the same thing as a randomized controlled trial?
No. Mendelian randomization is an observational design that approximates the logic of random allocation using inherited genetic variation rather than an actual intervention. Treat it as complementary evidence, strong enough to challenge a confounded observational association but not a substitute for a well-powered RCT when one is feasible and ethical.
How many genetic variants does a valid instrument need?
There is no fixed minimum. What matters is combined instrument strength, measured by the F-statistic, and independence between variants after linkage-disequilibrium clumping. Well-studied exposures such as LDL cholesterol or BMI have dozens to hundreds of genome-wide significant SNPs available, while a narrowly studied exposure may have only a handful, which increases reliance on any single method’s assumptions and makes the sensitivity battery even more important. Our simulation study on what the F-statistic actually tells you quantifies how much precision an MR design loses at each level of instrument strength.
What sample size gives adequate statistical power?
Power depends jointly on instrument strength, the share of exposure variance the instrument explains, and outcome GWAS sample size. As a practical rule, two-sample designs using an outcome GWAS with tens of thousands of cases for a binary outcome, or over 100,000 participants for a continuous outcome, are usually needed to detect a moderate causal effect with adequate precision. An underpowered analysis tends to produce a wide, inconclusive confidence interval rather than a false positive. Our validated power simulation, why Mendelian randomization papers get desk-rejected, puts numbers on this across six realistic study designs and shows how to report a minimum detectable effect alongside a null result.
What is multivariable Mendelian randomization used for?
Multivariable MR estimates the direct effect of one exposure on an outcome while holding one or more other, genetically correlated exposures constant, which is essential whenever two exposures share genetic architecture, such as LDL cholesterol and apolipoprotein B, or BMI and waist-to-hip ratio. The same framework doubles as a mediation-analysis tool, decomposing how much of a genetic effect on an outcome runs through a specified intermediate exposure rather than acting directly (Sanderson, 2021).
Can this method prove causation on its own?
Mendelian randomization provides strong evidence consistent with causation when all three instrumental-variable assumptions plausibly hold and multiple sensitivity analyses agree, but it cannot definitively prove causation by itself. No single observational method can. Current guidance treats convergent genetic and trial evidence as mutually reinforcing, and asks authors to report genetic findings with the same caution around residual pleiotropy that a trialist would apply to residual confounding (Burgess et al., 2023).
Do I need individual-level genotype data to run this kind of study?
Not for a two-sample design. A two-sample analysis can run entirely on publicly available GWAS summary statistics for the exposure and the outcome, which is why two-sample MR has become accessible to researchers without a genotyped cohort of their own and is a major reason for its rapid adoption outside specialist genetic-epidemiology groups.
Free Research Tools from Editverse
- GraphPro: build publication-ready charts, 25 types, with built-in t-test, ANOVA, correlation, and chi-square p-values. Free, no signup.
- StatPro: free statistical calculators and a test-selector tool covering group comparisons, categorical outcomes, time-to-event analysis, and diagnostic accuracy.
- Flowchart Pro: generate PRISMA 2020, PRISMA-ScR, CONSORT, STROBE, STARD, MOOSE, and ARRIVE flow diagrams directly in your browser.
Conclusion

Mendelian randomization gives researchers a way to approximate a randomized experiment from observational genetic data, which is why it has become the default response to reviewer concerns about confounding and reverse causation across epidemiology, cardiology, nutrition, and psychiatry. Applied well, with a justified instrument, transparent reporting of instrument strength, and a full battery of pleiotropy-robust sensitivity analyses reported alongside the primary IVW estimate, it produces some of the most persuasive observational causal evidence a manuscript can present. Applied carelessly, with one unchecked method and no STROBE-MR checklist, it is just as often the fastest route to a skeptical reviewer’s major revision. The LDL-C, vitamin D, and alcohol examples above show that range side by side, a genetic instrument that confirmed a drug target before the outcomes trial reported, one that sorted a long, confounded list of observational claims down to a specific, biologically coherent subset, and one that split a headline association into a real risk and a false one.
References
- Davey Smith G, Ebrahim S. ‘Mendelian randomization’: can genetic epidemiology contribute to understanding environmental determinants of disease? Int J Epidemiol. 2003;32(1):1-22. doi: 10.1093/ije/dyg070. PMID: 12689998.
- Sanderson E, Glymour MM, Holmes MV, et al. Mendelian randomization. Nature Reviews Methods Primers. 2022;2:6. doi: 10.1038/s43586-021-00092-5.
- Skrivankova VW, Richmond RC, Woolf BAR, et al. Strengthening the Reporting of Observational Studies in Epidemiology Using Mendelian Randomization: The STROBE-MR Statement. JAMA. 2021;326(16):1614-1621. doi: 10.1001/jama.2021.18236. PMID: 34698778.
- Burgess S, Butterworth A, Thompson SG. Mendelian randomization analysis with multiple genetic variants using summarized data. Genet Epidemiol. 2013;37(7):658-665. doi: 10.1002/gepi.21758. PMID: 24114802.
- Burgess S, Thompson SG. Avoiding bias from weak instruments in Mendelian randomization studies. Int J Epidemiol. 2011;40(3):755-764. doi: 10.1093/ije/dyr036. PMID: 21414999.
- Bowden J, Davey Smith G, Burgess S. Mendelian randomization with invalid instruments: effect estimation and bias detection through Egger regression. Int J Epidemiol. 2015;44(2):512-525. doi: 10.1093/ije/dyv080. PMID: 26050253.
- Bowden J, Davey Smith G, Haycock PC, Burgess S. Consistent estimation in Mendelian randomization with some invalid instruments using a weighted median estimator. Genet Epidemiol. 2016;40(4):304-314. doi: 10.1002/gepi.21965. PMID: 27061298.
- Verbanck M, Chen CY, Neale B, Do R. Detection of widespread horizontal pleiotropy in causal relationships inferred from Mendelian randomization between complex traits and diseases. Nat Genet. 2018;50(5):693-698. doi: 10.1038/s41588-018-0099-7. PMID: 29686387.
- Sekula P, Del Greco M F, Pattaro C, Köttgen A. Mendelian Randomization as an Approach to Assess Causality Using Observational Data. J Am Soc Nephrol. 2016;27(11):3253-3265. doi: 10.1681/ASN.2016010098. PMID: 27486138.
- Larsson SC, Butterworth AS, Burgess S. Mendelian randomization for cardiovascular diseases: principles and applications. European Heart Journal. 2023;44(47):4913-4924. doi: 10.1093/eurheartj/ehad736. PMID: 37935836.
- Lawlor DA, Tilling K, Davey Smith G. Triangulation in aetiological epidemiology. Int J Epidemiol. 2016;45(6):1866-1886. doi: 10.1093/ije/dyw314. PMID: 28108528.
- Burgess S, Davies NM, Thompson SG. Bias due to participant overlap in two-sample Mendelian randomization. Genet Epidemiol. 2016;40(7):597-608. doi: 10.1002/gepi.21998. PMID: 27625185.
- Burgess S, Davey Smith G, Davies NM, et al. Guidelines for performing Mendelian randomization investigations: update for summer 2023. Wellcome Open Research. doi: 10.12688/wellcomeopenres.15555.3.
- Ference BA, Yoo W, Alesh I, et al. Effect of long-term exposure to lower low-density lipoprotein cholesterol beginning early in life on the risk of coronary heart disease: a Mendelian randomization analysis. J Am Coll Cardiol. 2012;60(25):2631-2639. doi: 10.1016/j.jacc.2012.09.017.
- Pott J, Gådin JR, Theusch E, et al. Meta-GWAS of PCSK9 levels detects two novel loci at APOB and TM6SF2. Hum Mol Genet. 2022;31(6):999-1011. doi: 10.1093/hmg/ddab279. PMID: 34590679.
- Gagnon E, Gill D, Bourgault J, et al. RNA interference versus antibody-based PCSK9 inhibition for the prevention of cardiovascular disease: a drug-target Mendelian randomization study. Cardiovasc Res. 2025;121(7):1066-1075. doi: 10.1093/cvr/cvaf078. PMID: 40347490.
- Sanderson E. Multivariable Mendelian randomization and mediation. Cold Spring Harb Perspect Med. 2021;11(2):a038984. doi: 10.1101/cshperspect.a038984. PMID: 32341063.
- Fang A, Zhao Y, Yang P, Zhang X, Giovannucci EL. Vitamin D and human health: evidence from Mendelian randomization studies. Eur J Epidemiol. 2024;39(5):467-490. doi: 10.1007/s10654-023-01075-4. PMID: 38214845.
- Zhao SS, Mason A, Gjekmarkaj E, Yanaoka H, Burgess S. Associations between vitamin D and autoimmune diseases: Mendelian randomization analysis. Semin Arthritis Rheum. 2023;62:152238. doi: 10.1016/j.semarthrit.2023.152238. PMID: 37437450.
- Millwood IY, Walters RG, Mei XW, et al. Conventional and genetic evidence on alcohol and vascular disease aetiology: a prospective study of 500,000 men and women in China. Lancet. 2019;393(10183):1831-1842. doi: 10.1016/S0140-6736(18)31772-0. PMID: 30955975.
Related Resources
- Intention-to-Treat vs Per-Protocol Analysis: A Complete Guide for Clinical Researchers
- STROBE Guidelines Simplified: A Complete Tutorial for Reporting Observational Studies
- Causal Inference Impact on Epidemiology & Public Health
- Causal Inference in Observational Studies: Instrumental Variable Approaches
- Propensity Score Matching: Practical Tutorials for Observational Studies
- Mediation Analysis Unpacked: Causal Pathways in Health Interventions
- Statistical Methods in Genomics: From GWAS to Gene Expression Analysis
- Levels of Evidence in Clinical Research