Published | Last updated
A diagnosis tells you what a patient has. It does not tell you whether they can walk to the shops, use a phone, hold a job or get help at home. The ICF was built to describe exactly that, and it is the reason rehabilitation teams, outcome researchers and policy makers can compare functioning across conditions, settings and countries.
This guide explains the ICF components, codes and qualifiers, then shows the framework working on real data: a national survey of 114 stroke survivors in Iceland whose open dataset we recounted in R. It finishes with the Rehab-Cycle documentation tools, the ICF Core Sets, and a short method for linking your own questionnaire to the ICF.
Key Takeaways
- The ICF classifies functioning, not disease. It sits alongside the ICD: the ICD codes the diagnosis, the ICF codes what the person can do and what surrounds them.
- Four coded components plus personal factors. Codes start with b, s, d or e. Personal factors (age, sex, education, coping) are part of the model but are not classified.
- Qualifiers turn codes into measurements. A 0 to 4 scale rates the size of a problem; for environmental factors it also rates facilitators with a plus sign.
- Context changes the picture. In 114 stroke survivors with the same condition, 47% of those aged 75 and over used a walking device against 10% of those under 65, and 2% of the older group worked full-time against 45% of the younger group.
- You do not need all 1,400 categories. Core Sets and the 30-category ICF Rehabilitation Set give short, evidence-based lists to start from.
What the ICF Framework Is
The ICF was approved by the World Health Assembly in 2001 and belongs to the WHO family of international classifications.1 It replaced a purely medical view of disability with a biopsychosocial one: functioning is the result of an interaction between a health condition and two kinds of context, the environment and the person.2 Its two parts are functioning and disability (body, activities, participation) and contextual factors (environment and personal factors).
The classification holds more than 1,400 categories arranged in a hierarchy. A code such as b280 (sensation of pain) is a second-level category; b2801 (pain in body part) is one level deeper. Rehabilitation work rarely needs more than the second level, which is why short lists are so useful (see Core Sets below).
ICF Components, Prefixes and Example Codes
| Component | Prefix | Chapters | Example codes used in this guide |
|---|---|---|---|
| Body functions | b | 8: mental; sensory and pain; voice and speech; cardiovascular and respiratory; digestive and metabolic; genitourinary and reproductive; neuromusculoskeletal and movement; skin | b130 energy and drive; b280 sensation of pain; b455 exercise tolerance |
| Body structures | s | 8, mirroring the body-function chapters | s110 structure of brain |
| Activities and participation | d | 9: learning and applying knowledge; general tasks; communication; mobility; self-care; domestic life; interpersonal interactions; major life areas; community, social and civic life | d450 walking; d475 driving; d850 paid employment |
| Environmental factors | e | 5: products and technology; natural environment; support and relationships; attitudes; services, systems and policies | e115 products for daily living; e120 products for mobility; e580 health services |
| Personal factors | none | Not classified, because of wide social and cultural variation | Age, sex, education, habits, coping style |
Qualifiers: How a Code Becomes a Measurement
A code on its own only says that a domain is relevant. The qualifier says how big the problem is.1
| Qualifier | Meaning | Guide range of the problem |
|---|---|---|
| 0 | No problem (none, absent, negligible) | 0 to 4% |
| 1 | Mild problem | 5 to 24% |
| 2 | Moderate problem | 25 to 49% |
| 3 | Severe problem | 50 to 95% |
| 4 | Complete problem | 96 to 100% |
| 8 | Not specified | — |
| 9 | Not applicable | — |
The percentage ranges apply when a calibrated instrument exists; otherwise the clinician judges. Body-function codes carry one qualifier, the extent of the impairment; body-structure codes carry up to three (extent, nature of the change and location). Activities and participation carry two: performance (what the person does in their real environment, with any help they use) and capacity (what they could do without that help). A person who walks with a frame might be recorded as d450.23: a moderate problem in performance, a severe problem in capacity. For environmental factors the same scale rates a barrier, and a plus sign marks a facilitator, so e1201+3 reads as a substantial facilitator.
A Worked Example: 114 Stroke Survivors, Recounted in R
Olafsdottir and colleagues surveyed community-dwelling adults 1 to 2 years after a first stroke in Iceland.3 Hospital registers listed 454 admissions with a stroke diagnosis in 12 months; 203 people were eligible and 114 took part, a 56.2% response rate. The authors used the ICF linking rules to attach an ICF category to every survey item, then compared three age groups: under 65 (n = 29), 65 to 74 (n = 34) and 75 and over (n = 51). The paper is open access under CC BY 4.0 and ships the patient-level data, so we recounted every number in R.

Read Figure 1 as a documentation template. The health condition is the same for everyone in the sample, yet the four boxes around it hold the information a rehabilitation team can act on: fatigue and pain in body functions, driving and work in activities and participation, devices and living arrangements in the environment, and age, education and mood in personal factors. The authors treated the main post-stroke symptoms, such as balance problems, as personal factors because they described each person’s lived experience at 1 to 2 years.
Same Diagnosis, Different Context: What Changes With Age

Figure 2 shows where the age groups separated. The environmental items moved most:
- Walking device (e120): 47% of people aged 75 and over against 10% of those under 65 (24 of 51 against 3 of 29).
- Security buzzer (e115): 55% against 7%.
- Computer access (e130): 47% against 86%; smartphone access 33% against 83%.
- Full-time work (d850): 2% (1 of 51) against 45% (13 of 29).
- Anxiety or depression: 31% against 3%, with the 65 to 74 group at 3%.
Not every item rose with age. Balance problems were most common in the 65 to 74 group (76%, against 61% at 75 and over and 45% under 65), and the overall difference was modest (p = 0.038). A team that only looked at age bands would miss that.
Activities and Participation Scores
Participants also completed the Stroke Impact Scale, a patient-reported measure scored 0 to 100 where higher is better. Recounting the domain scores by age group gives the same pattern as the survey items: the oldest group scored lowest on daily activities, mobility and participation, while self-rated recovery did not differ.
| Stroke Impact Scale domain | Under 65 | 65 to 74 | 75 and over | ANOVA p |
|---|---|---|---|---|
| Daily activities (ADL/IADL) | 91.5 | 79.7 | 75.0 | 0.002 |
| Mobility | 90.1 | 78.9 | 70.3 | < 0.001 |
| Participation | 85.5 | 71.8 | 67.5 | 0.020 |
| Self-rated recovery | 81.4 | 73.1 | 71.8 | 0.143 |
Reading the Source Table
Figure 3 shows the paper’s own Table 2 for environmental factors, the kind of table you would produce when you report ICF-linked data.
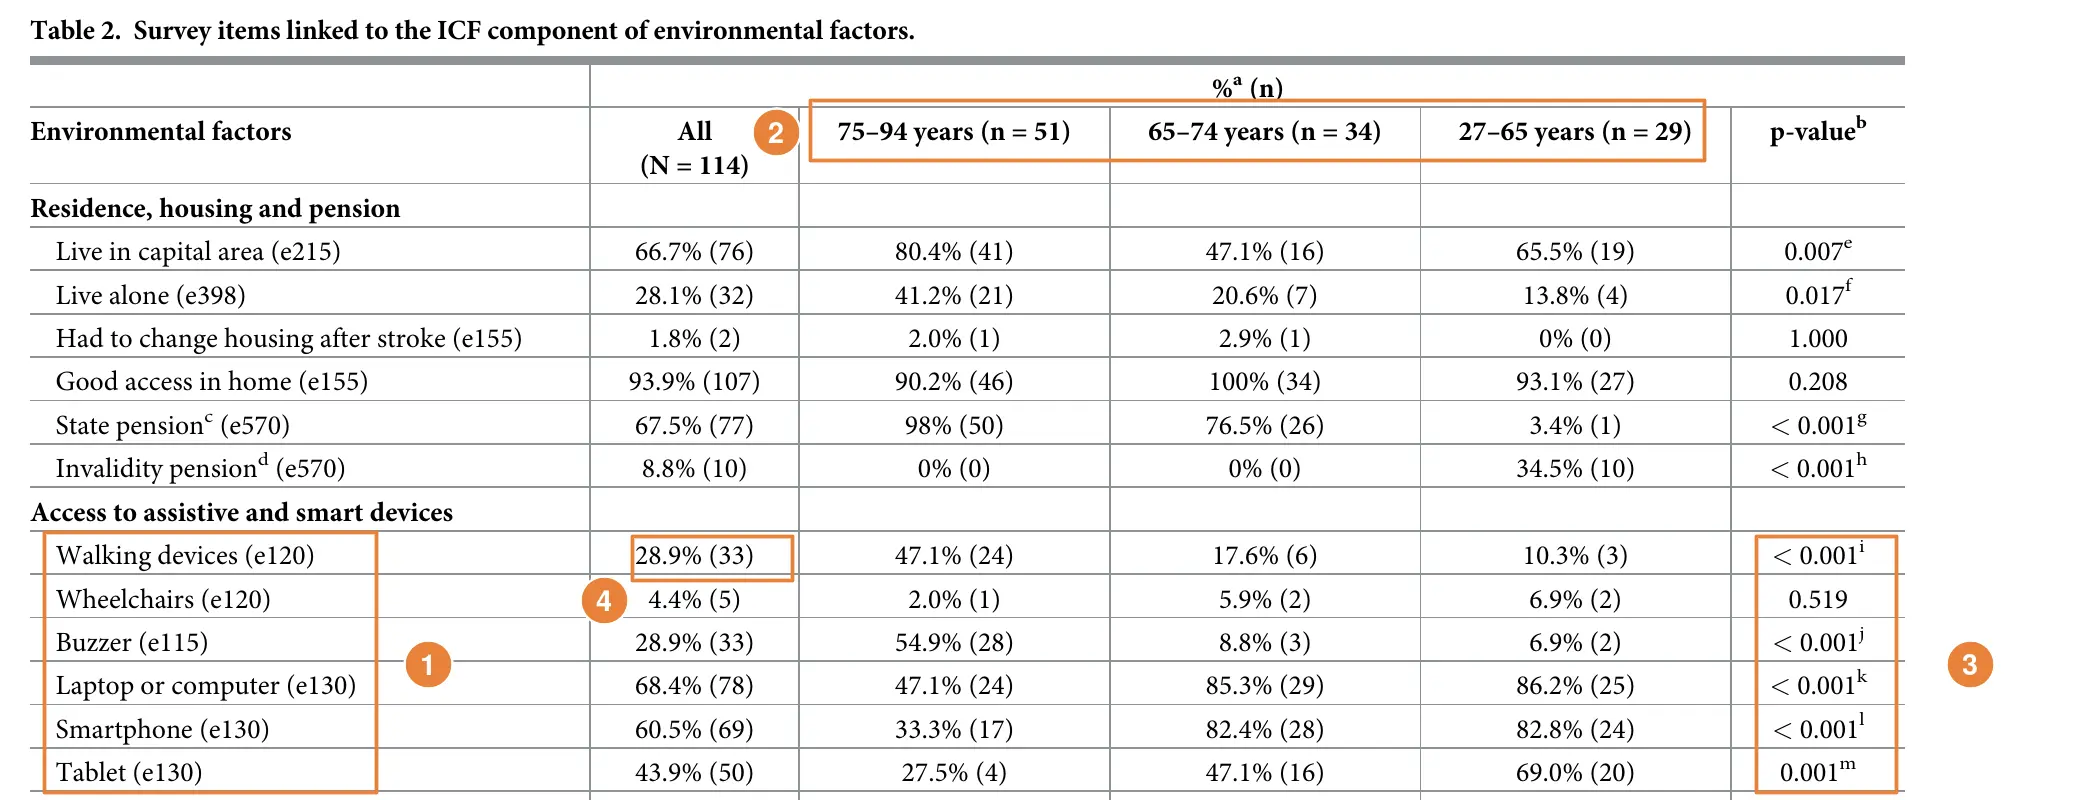
- 1Every item carries an ICF code. Walking devices are e120, the buzzer e115 and computers and smartphones e130 (products and technology for education). Another team might code smartphones under e125 (communication). That is why linking is a judgement and why the codes belong in the table.
- 2Age-group columns. The three columns give 75 and over (n = 51), 65 to 74 (n = 34) and the youngest group (n = 29). The table heading prints the youngest group as 27 to 65 while the text says under 65; our recount uses 27 to 64 and reproduces the published counts.
- 3P-values and letters. The authors used Fisher exact tests across the three groups; the superscript letters point to footnotes naming which pairs of age groups differ. Our recount agrees with the published conclusion for every item shown in Figure 2.
- 4Counts you can check. The bracketed counts let you recompute any percentage: 33 walking-device users is 24 + 6 + 3. Reporting counts next to percentages is what made this recount possible.
What did not reproduce. The paper reports a p-value of 0.013 for one or more falls in the previous 12 months. From the same counts (4 of 29, 12 of 34, 18 of 51) a Fisher exact test across the three groups gives 0.083, so we left falls out of Figure 2. For dependence on others for transport our patient-level column gives 26 people against the 27 in the published table, which includes people who relied on transport services; the p-value is the same (0.019).
Why Context Matters Beyond This Survey
A 2026 nationwide Korean cohort of 2,695 stroke survivors reached the same conclusion with a different design.4 The authors sorted predictors of social participation 12 months after stroke into the four ICF domains and analysed five Fugl-Meyer functional groups separately. In the most severely impaired group, environmental factors, home accessibility and caregiver characteristics were the main determinants; in higher-functioning groups, cognitive, language and psychosocial body functions and vocational status mattered more. The practical point for documentation is that the environment box deserves the same care as the impairment box, particularly for people with the greatest impairment.
Using the ICF in Clinical Documentation: The Rehab-Cycle
The Rehab-Cycle is a four-step problem-solving loop for rehabilitation: assessment, assignment, intervention and evaluation. Each step has an ICF-based documentation tool, so the same codes and qualifiers carry through from the first assessment to the final outcome.5
| Rehab-Cycle step | Question it answers | ICF-based tool |
|---|---|---|
| 1. Assessment | What is the person’s functioning state? | ICF Assessment Sheet: an overview of functioning that can combine the clinician’s and the patient’s view |
| 2. Assignment | Which problems become goals, and which targets do they point to? | ICF Categorical Profile: a visual profile of functioning at assessment, used to link goals to intervention targets |
| 3. Intervention | Who does what, with which resources? | ICF Intervention Table: coordinates interventions, roles and resources across the team |
| 4. Evaluation | What changed? | ICF Evaluation Display: functioning before and after the intervention |
The same model underlies the Rehabilitation Problem-Solving Form, which lets professionals analyse a patient’s problems, focus on specific targets and build the patient’s own perspective into decisions.6 ICF-based tools sit alongside patient-reported outcome measures; if you are choosing or validating one, see our guide to developing and validating patient-reported outcome measures.
ICF Core Sets and the ICF Rehabilitation Set
Coding the full classification is not realistic in a busy clinic. Core Sets are short lists of categories chosen through evidence and expert consensus for a health condition, and the ICF Rehabilitation Set does the same across conditions.
| Set | Size | Where it comes from |
|---|---|---|
| Comprehensive ICF Core Set for stroke | 130 second-level categories (41 b, 5 s, 51 d, 33 e) | Consensus conference of 39 experts from 12 countries, built on preliminary studies that identified 448 categories7 |
| Brief ICF Core Set for stroke | 18 categories (6 b, 2 s, 7 d, 3 e) | Same consensus process as the comprehensive set |
| ICF Rehabilitation Set | 30 categories (9 b, 21 d), plus a minimal set of 12 environmental factors | Regression analyses of data from 9,863 people with various health conditions, plus expert consultation8 |
A practical rule: start from the Brief Core Set for your condition or from the Rehabilitation Set, add the categories your service needs, and record qualifiers at baseline and again at follow-up so the Evaluation Display has something to compare.
How to Link Your Assessment or Survey to the ICF
Linking is how existing instruments and survey items are translated into ICF codes, as Olafsdottir and colleagues did for their 28-question survey. The published linking rules, updated in 2005 to eight rules in total, set out the procedure.9
- Split each item into meaningful concepts. One question can hold several concepts (for example, a device and the activity it supports).
- Link each concept to the most precise ICF category using the linking rules, not to a chapter heading.
- Label what the ICF does not cover (personal factors, the health condition, other content) instead of forcing a code.
- Have a second person link independently, compare the results and settle differences. The e125 versus e130 choice for smartphones in Figure 3 shows why.
- Publish the codes next to the results, as in Figure 3, and name the reporting guideline you followed; the Iceland authors followed STROBE. For studies that test the measurement properties of an instrument, the COSMIN reporting guideline applies.
If you are writing the questions yourself, see our guide to survey design and questionnaires before you collect data.
Writing Up a Rehabilitation or ICF Study? Consult Editverse
Editverse subject-matter experts work to COPE, ICMJE and GPP 2022 guidance, with institutional and country-specific ethics followed. Choose the stage you are at.

Editverse
Study Design
Planning an ICF-based survey or rehabilitation study? Fix the sampling, outcomes and linking plan before you collect data.
You send: your research question, setting and any draft questionnaire or protocol.
You get: guidance on design selection, outcome selection and measurement, sample size and bias mitigation.
When: standard turnaround is 3 to 5 business days.
Study Design Consultation · $400
Editverse
Statistical Analysis
Comparing age groups or sites on ICF items? Have the tests, intervals and tables done properly.
You send: your data, research questions and preferred software (SPSS, R or STATA).
You get: annotated code or syntax, complete output files, an interpretation guide and publication-ready tables.
When: standard turnaround is 4 to 6 business days.
SPSS/R/STATA Statistical Analysis · $400
Editverse
Manuscript Writing
Results in hand? Turn your ICF-based findings into a journal-ready paper.
You send: your outline, data, figures, tables and key references, plus the target journal.
You get: a full manuscript written by a subject-matter expert, with statistical review, journal formatting, cover letter and revision support until acceptance.
When: standard delivery is 15 days; express delivery is available.
Manuscript Writing Services · $1,500
Free Research Tools from Editverse
- Statistical Test Selector: choose the right test for comparing proportions or scores across age groups or sites.
- Sample Size Calculator: power analysis for the survey or cohort you are planning.
- Free Research Tools for Medical Researchers: the full set of browser-based tools.
Frequently Asked Questions
What is the ICF framework?
The International Classification of Functioning, Disability and Health (ICF) is a World Health Organization classification, approved by the World Health Assembly in 2001, that describes health through body functions and structures, activities and participation, and environmental factors, plus personal factors that are not coded. It describes how a person functions in daily life, not only which disease they have.
What are the components of the ICF?
The ICF has four coded components: body functions (b), body structures (s), activities and participation (d) and environmental factors (e). Personal factors, such as age, sex, education and coping style, are part of the model but have no codes. The health condition itself is classified separately, for example in the ICD.
What do the ICF qualifiers 0 to 4 mean?
A qualifier of 0 means no problem, 1 mild, 2 moderate, 3 severe and 4 complete problem, with 8 for not specified and 9 for not applicable. WHO gives guide ranges of 0 to 4%, 5 to 24%, 25 to 49%, 50 to 95% and 96 to 100% when calibrated instruments exist. For environmental factors the same scale rates barriers, and a plus sign marks facilitators, for example e1201+3.
What is the difference between capacity and performance in the ICF?
Performance is what a person actually does in their current environment, including help from assistive products or other people. Capacity is what they could do without that help. A person who walks with a frame might be coded d450.23: a moderate problem in performance and a severe problem in capacity.
How is the ICF different from the ICD?
The ICD classifies diseases and health conditions, the diagnosis. The ICF classifies functioning in that condition. Two people with the same stroke diagnosis can have very different ICF profiles, as the Iceland survey data in this guide show: walking-device use was 47% in people aged 75 and over and 10% in those under 65. WHO treats the two classifications as complementary.
What is an ICF Core Set?
An ICF Core Set is a short list of ICF categories selected for a health condition or setting through evidence and expert consensus. The stroke Core Sets, for example, have a Comprehensive version of 130 second-level categories and a Brief version of 18. The generic ICF Rehabilitation Set has 30 categories plus a minimal set of 12 environmental factors.
How do I link a questionnaire or survey to the ICF?
Use the published ICF linking rules, updated in 2005: split each item into meaningful concepts, link each concept to the most precise ICF category, and label concepts the ICF does not cover. Linking involves judgement, so report the codes in a table and, where possible, have two people link independently and settle differences.
Are personal factors coded in the ICF?
No. Personal factors such as age, sex, education, habits and coping style are recognised as part of the model but are not classified, because of wide social and cultural variation. Studies such as the Iceland stroke survey report them as plain descriptors beside the coded components.
References
- World Health Organization. International Classification of Functioning, Disability and Health (ICF). Geneva: WHO; 2001. who.int/standards/classifications
- Stucki G, Cieza A, Melvin J. The International Classification of Functioning, Disability and Health (ICF): a unifying model for the conceptual description of the rehabilitation strategy. J Rehabil Med. 2007;39(4):279–285. doi:10.2340/16501977-0041
- Olafsdottir SA, Hjaltadottir I, Galvin R, Hafsteinsdottir TB, Jonsdottir H, Arnadottir SA. Age differences in functioning and contextual factors in community-dwelling stroke survivors: a national cross-sectional survey. PLoS One. 2022;17(8):e0273644. doi:10.1371/journal.pone.0273644. Open access, CC BY 4.0; supplementary dataset S3 recounted by Editverse.
- Choi J, Han J, Lee HI, Sohn MK, Lee J, Kim DY, et al. Functional-level analysis of post-stroke social participation: a nationwide cohort study using the ICF framework. PLoS One. 2026;21(7):e0354691. doi:10.1371/journal.pone.0354691. Open access, CC BY 4.0.
- Rauch A, Cieza A, Stucki G. How to apply the International Classification of Functioning, Disability and Health (ICF) for rehabilitation management in clinical practice. Eur J Phys Rehabil Med. 2008;44(3):329–342. PMID:18762742
- Steiner WA, Ryser L, Huber E, Uebelhart D, Aeschlimann A, Stucki G. Use of the ICF model as a clinical problem-solving tool in physical therapy and rehabilitation medicine. Phys Ther. 2002;82(11):1098–1107. PMID:12405874
- Geyh S, Cieza A, Schouten J, Dickson H, Frommelt P, Omar Z, et al. ICF Core Sets for stroke. J Rehabil Med. 2004;(44 Suppl):135–141. doi:10.1080/16501960410016776
- Prodinger B, Cieza A, Oberhauser C, Bickenbach J, Üstün TB, Chatterji S, et al. Toward the International Classification of Functioning, Disability and Health (ICF) Rehabilitation Set: a minimal generic set of domains for rehabilitation as a health strategy. Arch Phys Med Rehabil. 2016;97(6):875–884. doi:10.1016/j.apmr.2015.12.030
- Cieza A, Geyh S, Chatterji S, Kostanjsek N, Üstün B, Stucki G. ICF linking rules: an update based on lessons learned. J Rehabil Med. 2005;37(4):212–218. doi:10.1080/16501970510040263
Related Resources
Editverse Research Team | Updated October 2026