
Every analysis of a failed hip implant, a malfunctioning infusion pump, or a robotic instrument that snapped mid-procedure starts with one question: which database actually recorded it? For medical devices in the United States the answer is the MAUDE database, short for Manufacturer and User Facility Device Experience, run by the FDA’s Center for Devices and Radiological Health. It is not NEISS. NEISS is the Consumer Product Safety Commission’s emergency department sample for consumer product injuries, and it contains no device failure reports and no litigation records of any kind. Getting that right at the protocol stage is the difference between a study that reaches peer review and one that collapses when a reviewer asks where the denominator came from.
In Simple Words
MAUDE is a pile of complaint reports about medical devices, not a survey. It tells you what has gone wrong and how, but not how often, because nobody counts the devices that worked. Use it to find failure modes and generate hypotheses. Do not use it to publish a rate.
Correction notice
An earlier version of this article described device failure reports and settlement values as contents of NEISS. That was wrong on both counts, and it also cited a 1999 Institute of Medicine book chapter as a 2023 study. Those claims have been removed and the article rebuilt around the database that does hold device failure reports.
What the MAUDE Database Actually Contains
MAUDE is the public face of the FDA’s medical device reporting system. Each record is one medical device report, or MDR, describing a suspected device-associated death, serious injury, or malfunction. FDA states that it receives over two million medical device reports each year, publicly available in MAUDE since 1999.
Three facts shape every design decision that follows. First, the MAUDE search interface is a rolling ten-year window, refreshed monthly. If your question spans twenty years, the search box will silently truncate you. Second, the downloadable MDR data files reach much further back and sit separately: voluntary reports from June 1993, user facility reports from 1991, distributor reports from 1993, and manufacturer reports from August 1996, joined across seven file types on the MDR report key. Legacy Device Experience Network reports for 1984 to 1996 live on the same page, as do the Alternative Summary Reporting files discussed below. Third, two redaction tokens will appear in your text fields: under the Freedom of Information Act, trade secret information is replaced with “(b)(4)” and personal or medical information with “(b)(6)”. Treat those as structured missingness, not noise.
One more note for anyone writing a methods section in 2026: FDA has stated that MAUDE data will move into the agency’s Adverse Event Monitoring System during 2026. Name the interface and the extraction date you used.
Who Reports to MAUDE, and Under What Rules
The obligations sit in 21 CFR Part 803. Manufacturers, importers, and device user facilities are mandatory reporters. Clinicians, patients, and consumers report voluntarily through MedWatch. As Batheja and colleagues note, that open platform widens the scope of collection and simultaneously widens the scope for bias.
How lopsided is the mix? Dallas and colleagues answered this for transvaginal mesh. Across 40,266 mesh safety reports filed between 2000 and 2017 they reviewed a random 2 percent sample of 900 in depth: 46 percent came from the manufacturer, 41 percent from an attorney, 10 percent from a healthcare provider, and 2 percent from patients. Within four years of submission, 18.6 percent had been modified at least once. A database where four in ten reports on a litigated device arrive from law firms tracks legal activity as much as clinical activity. Zou and colleagues found the mirror image for Essure: of 4,994 eligible reports filed in a ten-month window in 2018, more than 90 percent came from the manufacturer.
NEISS vs MAUDE vs Recall Databases: Which One Answers Your Question
This is the comparison that saves the most wasted months. The three systems look similar from a distance and answer entirely different questions. For the mechanics of how a NEISS record is created in the first place, see how an ER visit becomes a NEISS record.
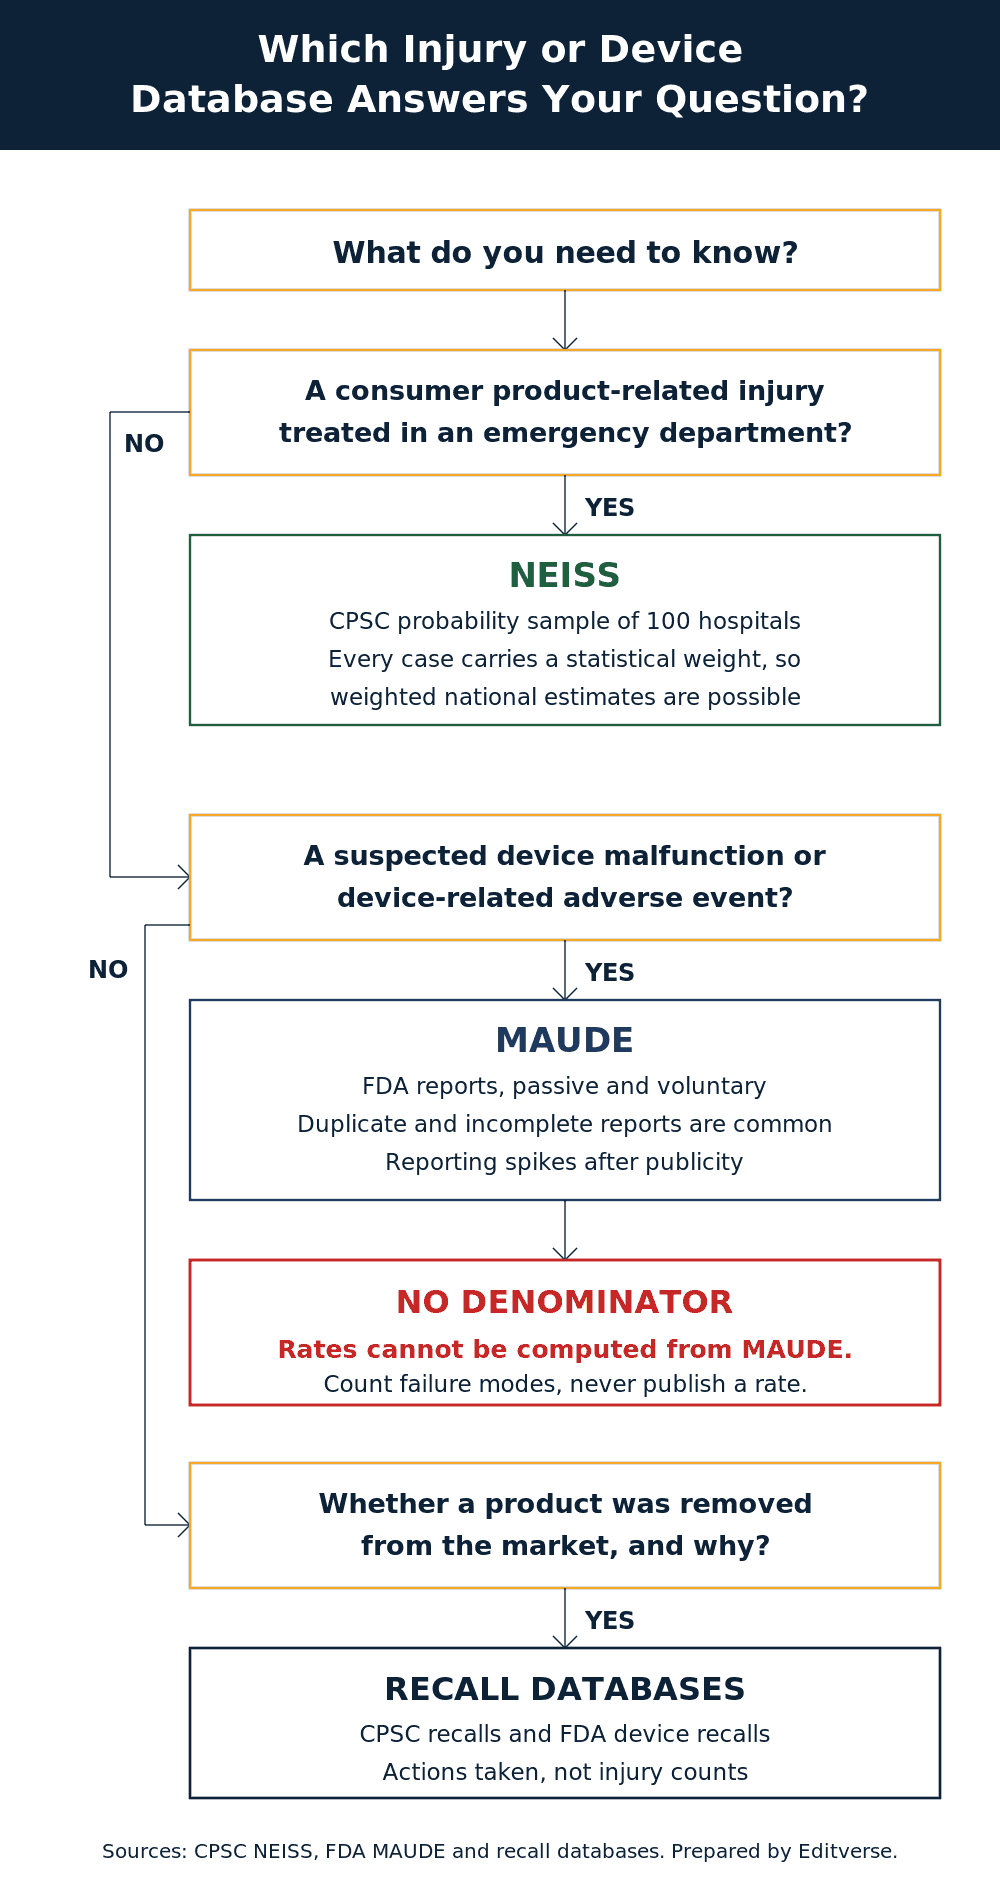
| Question | NEISS (CPSC) | MAUDE (FDA) | FDA device recall database |
|---|---|---|---|
| What is one record? | One emergency department visit for an injury associated with a consumer product | One report of a suspected device-associated death, serious injury, or malfunction | One firm-initiated or FDA-requested correction or removal action |
| Study design | Stratified probability sample of 100 hospital emergency departments | Passive spontaneous reporting, no sampling frame | Regulatory action register |
| Is there a denominator? | Yes. Every case carries a statistical weight that scales to a national estimate | No. Devices used without incident are never recorded | No |
| Can you compute a rate? | Yes, with the design variables and CPSC’s reportability rules applied | No. FDA states MDR data is not intended to evaluate rates of adverse events | No |
| Coding system | CPSC internal body part, diagnosis, product, disposition and location codes. Not ICD | FDA device problem and health effect codes, plus product code and brand | Recall class, reason for recall, product code |
| Free-text narrative | Yes, capped at 400 characters | Yes, uncapped but redacted and highly variable | Short structured reason field |
| Covers implanted and clinical devices? | No. Consumer products only | Yes. This is its entire remit | Yes |
| The question it answers well | How many US emergency department visits are associated with product X, nationally? | What failure modes and harms have been reported for device X, and how do they cluster? | Has device X been corrected or removed, why, and how serious did FDA judge it? |
The recall database is the one most researchers forget, and it is often the cheapest way to strengthen a MAUDE paper, because a recall is an adjudicated regulatory judgment with a date attached, which gives you an exogenous event to analyse around. Velasquez Ospina and colleagues did exactly that with urological lasers, comparing 954 adverse events across thulium fibre and holmium:YAG systems from 2018 to 2024 and showing that reported Level II and Level III events for thulium fibre lasers fell significantly after FDA’s 2021 Class II recall.
If your question concerns a consumer product rather than a regulated device, you are in NEISS territory, and the practical issue becomes whether NEISS injury statistics are reliable for your specific estimate. Two related questions, what FDA clearance actually proves about a device and the testing standards that sit upstream of these failures, are worth reading before you frame a device safety paper.
Seven Documented Weaknesses of the MAUDE Database
None of these are secret. Most are stated by FDA on its own documentation page, and every one has been quantified in the peer-reviewed literature. Reviewers know them. Address them before someone else does.
1. There is no denominator, so there is no rate
FDA’s position is unambiguous. Its official MAUDE documentation states that MDR data “is not intended to be used either to evaluate rates of adverse events, evaluate a change in event rates over time, or to compare adverse event occurrence rates across devices,” because incidence, prevalence and cause “cannot be determined from this reporting system alone due to under-reporting of events, inaccuracies in reports, lack of verification that the device caused the reported event, and lack of information about frequency of device use.”
Ziapour and colleagues put it operationally after reviewing 58 cardiovascular surgery studies built on MAUDE: an incidence rate needs both the event-free cases and the adverse events among all patients using a device, and neither variable exists in MAUDE. Chughtai and colleagues then reviewed 11 MAUDE studies of prostate devices and found 9 of the 11 had used the number of adverse events or malfunctions as the denominator, which is a rate of events among events. If your plan involves any per-patient rate, check our primer on incidence versus prevalence and confirm your denominator exists.
2. Reporting is passive, and under-reporting is measurable
The clearest quantification comes from the POTTER-AF 3 study. Tilz and colleagues compared MAUDE against an invitation-based multicentre registry for the same rare complication, oesophageal fistula after atrial fibrillation ablation, over the same period from August 2009 to August 2019. MAUDE held 47 cases; the registry held 81. Completeness diverged just as sharply: the diagnostic method was reported for 38.3 percent of MAUDE cases against 98.8 percent in the registry, and treatment for 57.4 percent against 100 percent. Friedman and colleagues reached the same conclusion from the other direction, tallying 565 da Vinci instrument failures across 528 reports while stating plainly that a true failure rate cannot be determined from these data.
3. One event can generate several records
This is structural, not accidental. FDA’s documentation explains that a distinct master event record is created for each source reporting an event, so if a user facility, a distributor, a manufacturer, and a voluntary submitter all report one incident, four event records exist. Sandberg and colleagues measured the cost across the 1,103 reports that prompted FDA’s 2008 transvaginal mesh public health notification: 64 contained duplicated information, six represented multiple patients, 47 percent identified no reporter source, and at least 28 percent of the devices were no longer on the US market. A credible study needs a documented de-duplication rule and must state how many records it removed.
4. Key fields are missing, redacted, or never verified
Whitford and colleagues examined wheelchair injury reports from 2014 to 2018 and found that in 55.17 percent of included reports the wheelchair itself was unavailable for evaluation, while manufacturers’ submission lag after notification ranged from 3 to 159 days. They described inherent weaknesses in the reporting process and a concerning level of reporting bias. Add the FOIA redactions above and the practical position is that a MAUDE record is a claim, not a verified observation.
5. Report volume moves with publicity, litigation, and recalls
FDA says this itself, noting that event counts may fluctuate for reasons that do not reflect a change in the actual rate, specifically naming changes in technology that affect how often a device is used, changes in a firm’s reporting processes, and public communications or media reports about a technology. Naumann and Brown documented the artefact for electromechanical morcellation: across a decade they found 9 deaths and 215 injury or delay events, and morcellation of a previously undiagnosed malignancy was first reported only in December 2013, immediately before the issue became a national story. Their conclusion is the one to carry: MAUDE detects perioperative events reasonably well but is poor at detecting late events after surgery, and outcome registries track long-term harm more efficiently.
6. Alternative Summary Reporting kept reports out of MAUDE until 2019
This is the historical fact that invalidates many older time series. FDA ran an Alternative Summary Reporting programme from 1997 through June 2019, under which manufacturers could file certain well-characterised events for specific devices as summaries rather than individual MDRs. Those reports never entered MAUDE. FDA ended the programme in June 2019 and revoked all such exemptions, and the reports received from 1999 through April 2019 are now published as legacy files.
Benham and colleagues quantified the gap for general surgery devices over 1999 to 2018: 283,308 malfunction reports in public MAUDE against 109,954 in the non-public system. For surgical staplers and clip appliers, roughly 80 percent of reports sat in the alternative system and only 20 percent in MAUDE, and those records carried no injury or death information at all, whereas 42.9 percent of general surgical device malfunctions in MAUDE resulted in patient injury or death. If your window crosses 2019 and you have not accounted for this, an apparent surge in reports may be nothing more than the programme ending.
7. The clinical detail lives in unstructured free text
Coded fields give you the device and a broad problem category. Everything a clinician wants to know sits in the narrative, written by different reporters to no common standard. Davies and colleagues screened 5,645 records for their systematic review of otology studies using MAUDE, included the 8 that qualified, and rated every one poor quality, attributing this primarily to MAUDE’s structural limitations as a passive surveillance system built on non-standardised free-text reports. The methodological response is text processing: Shah and colleagues describe an extract, transform and load pipeline built on the openFDA API combined with a large language model, explicitly motivated by the observation that MAUDE studies frequently report unclear extraction methods. The challenges will look familiar from our piece on the free-text narrative field in injury surveillance.
What a Published MAUDE Database Study Actually Looks Like
The strongest MAUDE papers share one habit: they ask a question that does not require a denominator. Four worked examples, all real, all with PMIDs you can check.
Comparative failure profile between two technologies. Cho and colleagues analysed 1,237 MAUDE reports on pulsed field and radiofrequency ablation catheters over seven months of 2024, reporting the proportion of reported adverse events that were deaths as 2.6 percent for pulsed field against 8.9 percent for radiofrequency (P = 0.010), with haemolysis in 9.0 percent versus 0 percent and mechanical catheter problems in 87.2 percent versus 17.2 percent. Note the framing throughout: proportions of reported events, never rates per procedure.
Mortality characterisation over a long window. Reddy and colleagues reviewed stapler and clip applier reports from 1992 to 2016 under six FDA product codes, identifying 75,415 malfunctions, 21,115 injuries, and 676 deaths, 76.3 percent of them postoperative. They adjusted for annual surgical case volume using an external source, the Healthcare Cost and Utilization Project, which is the correct instinct when MAUDE cannot supply the denominator itself.
Failure-mode taxonomy. Friedman and colleagues classified 565 da Vinci instrument failures into five engineering categories: wrist or tool tip (285), cautery (174), shaft (76), cable (29), and control housing (7). This is exactly what MAUDE is built for, because the outcome of interest is the structure of the failures, not their frequency.
An honest attempt at an external denominator. Ferguson and Lin analysed artificial pancreas systems and reported adjusted event rates per 100,000 units by manufacturer rather than raw counts. Whether those denominators are the right ones is arguable, but the paper confronts the problem rather than pretending it does not exist.
One counterpoint is worth knowing. Galper and colleagues applied natural language processing to MAUDE reports for transcatheter aortic valve replacement and MitraClip and compared the resulting event rates against the Transcatheter Valve Therapy registry, reporting close correlation (R-squared 0.86 and 0.77) and no significant difference for any event except bleeding. That is genuine, and also the exception: a high-volume, closely tracked, mandatorily registered procedure is close to the best case for MAUDE.
How to Design a Defensible MAUDE Database Study
Fix the exposure before you touch the data. Decide whether you are querying by FDA product code, brand name, manufacturer, or a combination, and write it down. Product codes are more stable; brand-name searches catch reports that product codes miss and pull in irrelevant ones. Most published studies do both and report the overlap.
Choose your extraction route and record it. The web interface gives ten years; the bulk files give the full history but require joining seven file types. The openFDA device event API is the route to prefer, because it is the only one that produces a re-runnable extraction. Record the extraction date: MAUDE refreshes monthly and your counts will not reproduce next month.
De-duplicate explicitly and report the loss. Decide in advance how you will handle supplemental reports, multi-source reports of one event, and reports describing multiple patients. Publish records retrieved, excluded at each step, and analysed.
Check the recall context. Query the FDA medical device recall database and the Total Product Life Cycle tool for your product codes over the same window. A recall inside your study period is either a confounder you must handle or the natural experiment your paper is actually about.
Code the narratives twice and report agreement. Blind double-coding with a kappa statistic is the cheapest single thing that lifts a MAUDE paper from poor to acceptable on the appraisal tools reviewers use. If you use machine learning, hold out a manually coded validation set.
Report proportions of reported events, never population rates. Say “of reported events, X percent were Y” and mean it. If you need an external denominator, name it, justify it, and treat the result as an approximation with a stated direction of bias.
Write the limitations paragraph from FDA’s own language. Quoting the agency on rates, under-reporting, and causality is stronger than paraphrasing it. The STROBE checklist for observational studies is what most journals expect, and its bias and generalisability items are exactly where a MAUDE study has to do its work. Our discussion of the limitations of observational real-world data covers the same ground for registry and claims sources.
Common Mistakes in MAUDE Database Research
- Publishing a rate. The commonest error and the fastest route to rejection. Chughtai and colleagues found 9 of 11 studies doing it.
- Reading a rise in reports as a rise in harm. Reporting volume responds to publicity, litigation, recalls, and changes in how a firm processes complaints. FDA says so explicitly.
- Crossing 2019 without mentioning Alternative Summary Reporting. Any trend line spanning the end of that programme has a structural break in it.
- Treating a death field as an attributed death. FDA notes a narrative may contain the word “death” without the report being classified as one, and that submitting an MDR does not itself demonstrate the device caused the outcome.
- Ignoring the redaction tokens. “(b)(4)” and “(b)(6)” are systematic, not random, so dropping those records changes your sample.
- Borrowing survey logic from the wrong database. MAUDE has no weights, strata, or primary sampling units, so there is nothing to declare to a survey package. That machinery belongs to NEISS and NHANES, where getting it wrong genuinely moves the answer, as we showed in why survey weights change the answer.
- Calling the finding causal. A device named in a report is a device present at an event.
Tools and Resources
Everything you need to run a MAUDE study is free. The search interface is fastest for scoping, the MDR data files hold the full history, and the openFDA API is what you want for anything reproducible. For the consumer-product comparison, CPSC publishes the NEISS documentation and FAQ alongside free annual data files. If your analysis ends in a rate that does have a real denominator behind it, our free incidence rate calculator will handle the confidence interval.
Free Research Tools from Editverse
- GraphPro: build publication-ready charts, 25 types, with built-in t-test, ANOVA, correlation, and chi-square p-values. Free, no signup.
- StatPro: free statistical calculators and a test-selector tool covering group comparisons, categorical outcomes, time-to-event analysis, and diagnostic accuracy.
- Flowchart Pro: generate PRISMA 2020, PRISMA-ScR, CONSORT, STROBE, STARD, MOOSE, and ARRIVE flow diagrams directly in your browser.
Professional Support for a Device Safety Study
The failure mode for a MAUDE project is rarely the analysis. It is discovering at write-up that the question was already answered, that the device codes you need do not span the years you want, or that the analytic sample cannot support the comparison. Cheap problems to find at the protocol stage, expensive ones at submission.
Start here
$450
Feasibility and protocol assessment. Checks whether your question has already been published, whether the fields you need exist across the years you want, and whether the analytic sample can support the estimate. Credited in full against any study you commission. 5 business days.
Registry study
$2,400
NTDB and TQP trauma registry study. Risk-adjusted outcomes across centres, with severity treated as derived rather than measured and facility clustering modelled. You supply the data under your ACS agreement. 15 business days.
Custom scope
From $3,500
Extended and multi-database registry study. For multi-year trend work, linkage between two data sources, or prediction models with external validation. Quoted, typically from $3,500, with a fixed written scope before any work begins.
Everything in this category is listed under Registry and Real-World Data Studies. If you already hold your extract and only need the statistics run and reported to journal standard, the Just Data Service is the narrower engagement. And if you are still deciding between MAUDE, a registry, and a claims source, start with our guide to which health database your study should use.
Frequently Asked Questions About the MAUDE Database
Does the NEISS database contain medical device failure reports?
No. NEISS is the Consumer Product Safety Commission’s National Electronic Injury Surveillance System, a stratified probability sample of 100 hospital emergency departments recording injuries associated with consumer products. It holds no medical device failure reports, no manufacturer complaint records, and no litigation or settlement data. Medical device adverse events and malfunctions are reported to the FDA and published in MAUDE.
Can I calculate an adverse event rate from the MAUDE database?
No. FDA states that MDR data is not intended to be used to evaluate rates of adverse events, to evaluate a change in event rates over time, or to compare adverse event occurrence rates across devices. The reason is structural: devices used without incident are never recorded, so there is no denominator. Report proportions of reported events instead, or bring in an external denominator such as procedure volume and state its limitations.
How far back does MAUDE data go?
The public web search interface holds the last ten years of reports and is updated monthly. The downloadable MDR data files reach further: voluntary reports from June 1993, user facility reports from 1991, distributor reports from 1993, and manufacturer reports from August 1996, with legacy Device Experience Network reports covering 1984 to 1996 published separately.
What was the Alternative Summary Reporting programme and why does it matter for research?
Between 1997 and June 2019, FDA allowed manufacturers to file certain well-characterised events for specific devices as summary reports rather than individual MDRs, and those reports never appeared in MAUDE. FDA ended the programme in June 2019 and revoked the exemptions, publishing the 1999 to April 2019 reports as legacy files. Benham and colleagues found roughly 80 percent of surgical stapler and clip applier malfunction reports had gone to that system, so any trend analysis crossing 2019 needs to account for the change.
Are MAUDE database studies publishable in peer-reviewed journals?
Yes, and hundreds have been. The quality bar is the problem rather than acceptance. Two systematic reviews found most published MAUDE studies to be of poor quality on standard appraisal tools, mainly because of non-consecutive case selection, unclear outcome measures, absent follow-up, and inappropriate rate calculation. A study that pre-specifies its query, de-duplicates transparently, double-codes narratives, and reports proportions rather than rates clears that bar.
Should I use MAUDE or a clinical registry for a device safety question?
Use MAUDE to discover failure modes, characterise the shape of reported harm, and generate hypotheses quickly and for free. Use a registry when you need incidence, long-term outcomes, or a denominator. The POTTER-AF 3 comparison found fewer cases and substantially poorer data completeness in MAUDE than in a matched voluntary registry for the same complication over the same period.
Conclusion
The MAUDE database is genuinely useful and routinely misused, and the two facts are connected. It is free, it is fast, it is the only public national record of medical device failure in the United States, and it will happily return a number that looks like a rate to anyone who does not know that no denominator exists. Researchers who publish well from it treat it as a passive complaint archive with a rich free-text layer: they ask what went wrong and how failures cluster, not how often. They de-duplicate on the record, name their extraction date, account for the 2019 break, and write their limitations in FDA’s own words. Do that and MAUDE will carry a paper.
References
- US Food and Drug Administration. About Manufacturer and User Facility Device Experience (MAUDE) Database. Silver Spring: FDA. Available from: fda.gov
- US Food and Drug Administration. MDR Data Files. Silver Spring: FDA. Available from: fda.gov
- Medical Device Reporting. 21 CFR Part 803. Available from: ecfr.gov
- Ziapour B, Zaepfel C, Iafrati MD, Suarez LB, Salehi P. A systematic review of the quality of cardiovascular surgery studies that extracted data from the MAUDE database. J Vasc Surg. 2021;74(5):1708-1720.e5. PMID: 33600931. doi:10.1016/j.jvs.2021.01.050
- Davies C, Nieri CA, Sheyn A, Rangarajan S, Yawn RJ. The use and utility of Food and Drug Administration adverse event data from the Manufacturer and User Facility Device Experience database in otology: a systematic review. Otol Neurotol. 2023;44(6):534-541. PMID: 37254239. doi:10.1097/MAO.0000000000003899
- Chughtai B, Venkatraman G, Gressler L, Elterman D, Bhojani N. The role of manufacturer and user facility database in evaluating BPH and prostate cancer procedures. World J Urol. 2025;44(1):24. PMID: 41351682. doi:10.1007/s00345-025-05987-6
- Batheja A, Bentan M, Coelho DH. Considerations for use of the MAUDE database in otolaryngology-head and neck surgery research. Otolaryngol Head Neck Surg. 2024;171(1):320-322. PMID: 38327259. doi:10.1002/ohn.666
- Dallas K, Souders CP, Caron A, Clark K, Obi N, McClelland L, et al. Manufacturer and User Facility Device Experience reporting of events related to transvaginal mesh: understanding the data. Female Pelvic Med Reconstr Surg. 2022;28(5):332-335. PMID: 35421039. doi:10.1097/SPV.0000000000001177
- Sandberg JM, Gray I, Pearlman A, Terlecki RP. An evaluation of the Manufacturer and User Facility Device Experience database that inspired the United States Food and Drug Administration’s reclassification of transvaginal mesh. Investig Clin Urol. 2018;59(2):126-132. PMID: 29520389. doi:10.4111/icu.2018.59.2.126
- Benham DA, Calvo RY, Carr MJ, Diaz JA, Sise CB, Sise MJ, et al. Revealing the scope of surgical device malfunctions: analysis of the “hidden” Food and Drug Administration device database. Am J Surg. 2021;221(6):1121-1126. PMID: 33745689. doi:10.1016/j.amjsurg.2021.03.017
- Tilz RR, Purerfellner H, Kuck KH, Merino JL, Schmidt V, Vogler J, et al. Underreporting of complications following AF ablation: comparison of the Manufacturer and User Facility Device Experience FDA database and a voluntary invitation-based registry: the POTTER-AF 3 study. Heart Rhythm. 2025;22(6):1472-1479. PMID: 39353499. doi:10.1016/j.hrthm.2024.09.060
- Naumann RW, Brown J. Complications of electromechanical morcellation reported in the Manufacturer and User Facility Device Experience (MAUDE) database. J Minim Invasive Gynecol. 2015;22(6):1018-1021. PMID: 25987522. doi:10.1016/j.jmig.2015.05.008
- Della Badia C, Nyirjesy P, Atogho A. Endometrial ablation devices: review of a manufacturer and user facility device experience database. J Minim Invasive Gynecol. 2007;14(4):436-441. PMID: 17630160. doi:10.1016/j.jmig.2007.05.008
- Whitford M, Mitchell SJ, Marzloff GE, Zindle JK, Richmond MA, Bogie KM, et al. Wheelchair mobility-related injuries due to inadvertent lower extremity displacement on footplates: analysis of the FDA MAUDE database from 2014 to 2018. J Patient Saf. 2021;17(8):e1785-e1792. PMID: 32217931. doi:10.1097/PTS.0000000000000633
- Friedman DCW, Lendvay TS, Hannaford B. Instrument failures for the da Vinci surgical system: a Food and Drug Administration MAUDE database study. Surg Endosc. 2013;27(5):1503-1508. PMID: 23242487. doi:10.1007/s00464-012-2659-8
- Reddy BN, Subhash M, Vangel M, Markowiak S, Delvadia D, Razdan S, et al. Mortality related to the use of stapler devices and clip appliers: analysis of the Food and Drug Administration Manufacturer and User Facility Device Experience database. Surgery. 2023;173(5):1184-1190. PMID: 36564288. doi:10.1016/j.surg.2022.11.013
- Cho MS, Lee SR, Black-Maier E, Jackson KP, Friedman DJ, Pokorney SD, et al. Complications associated with pulsed field ablation vs radiofrequency catheter ablation of atrial fibrillation. Heart Rhythm. 2025;22(9):2194-2200. PMID: 39515491. doi:10.1016/j.hrthm.2024.10.063
- Velasquez Ospina J, Gozlan E, Williams A, Rathinam A, Khandekar A, Katz J, et al. Thulium fiber vs. holmium:YAG lasers in urology: insights from the FDA MAUDE database. World J Urol. 2025;43(1):593. PMID: 41045396. doi:10.1007/s00345-025-05919-4
- Zou C, Davis B, Wigle PR, Hincapie AL, Guo JJ. Safety reporting of Essure medical device: a qualitative and quantitative assessment on the FDA Manufacturer and User Facility Device Experience database in 2018. Front Reprod Health. 2023;5:1172927. PMID: 37519343. doi:10.3389/frph.2023.1172927
- Ferguson AM, Lin AC. Themes, rates, and risk of adverse events of the artificial pancreas in the United States using MAUDE. Ann Biomed Eng. 2024;52(8):2282-2286. PMID: 38740730. doi:10.1007/s10439-024-03529-6
- Galper BZ, Beery DE, Leighton G, Englander LL. Comparison of adverse event and device problem rates for transcatheter aortic valve replacement and MitraClip procedures as reported by the Transcatheter Valve Therapy Registry and the Food and Drug Administration postmarket surveillance data. Am Heart J. 2018;198:64-74. PMID: 29653650. doi:10.1016/j.ahj.2017.10.013
- Shah F, Yu Y, Shi Y, Gong Y. Leveraging data pipeline and LLM to advance patient safety event studies. Stud Health Technol Inform. 2025;327:253-257. PMID: 40380434. doi:10.3233/SHTI250323
- Navon L, Chen LH, Cowhig M, Wolkin AF. Two decades of nonfatal injury data: a scoping review of the National Electronic Injury Surveillance System-All Injury Program, 2001-2021. Inj Epidemiol. 2023;10(1):44. PMID: 37679835. doi:10.1186/s40621-023-00455-4
- Thompson MC, Wheeler KK, Shi J, Smith GA, Xiang H. An evaluation of comparability between NEISS and ICD-9-CM injury coding. PLoS One. 2014;9(3):e92052. PMID: 24658100. doi:10.1371/journal.pone.0092052
- Shields W, Dong Y, Jager L, Shiang E, Frattaroli S, Omaki E. Using the NEISS database to understand pressure cooker related injuries in the USA. Inj Prev. 2023;29(6):506-510. PMID: 37666516. doi:10.1136/ip-2023-044910