Published | Last updated
The limits of agreement method, also called Bland-Altman analysis, is the standard way to judge whether two measurement methods can be used interchangeably. The original paper by Bland and Altman appeared in The Lancet in 1986 and has been cited tens of thousands of times: OpenAlex records 47,910 citations and Crossref 38,854 as of 28 October 2026 [1]. This guide shows the calculation on the original peak flow data, checks every number against Bland’s own page, and explains what the result does and does not prove.
On this page: Why correlation fails · The calculation · Worked example · How to read it · Reporting · Related methods · Common mistake · FAQ
Why correlation and regression are not enough for method comparison
Bland and Altman gave several reasons why the correlation coefficient measures the wrong thing. Correlation shows the strength of a relationship, not agreement. A test of significance is irrelevant to agreement, because it would be surprising if two methods designed to measure the same quantity were unrelated. And data in poor agreement can still produce high correlations [1,2].
Their examples are worth knowing. Two methods of measuring gestational age had a correlation of 0.85, even though babies of 35 weeks by one method ranged from 34 to 39.5 weeks by the other. Two Wright peak flow meters tested by another group had a correlation of 0.992, and 0.996 when connected in series so that both measured the same flow. And in their own data, a correlation of 0.94 concealed considerable lack of agreement (Figure 1) [2].

How the limits of agreement are calculated
For each subject, subtract one method from the other and average the two readings. Then work with the differences.
- Difference: d = method A minus method B, for every subject. State the direction and keep it.
- Mean of the pair: (A + B) / 2, for the horizontal axis. Bland and Altman say to plot differences against the mean of the two, because plotting against either method alone builds in a statistical artefact [2].
- Bias: the mean of the differences, written d-bar.
- Spread: the standard deviation s of the differences.
- Limits of agreement: d-bar − 1.96 s and d-bar + 1.96 s.
- Precision: the standard error of d-bar is s divided by the square root of n. The standard error of each limit is larger: Bland and Altman give about the square root of 3s²/n in 1986, and a more exact form, the square root of s²(1/n + 1.96²/(2(n−1))), in 1999 [2,3]. Confidence intervals use the t distribution with n−1 degrees of freedom.
One detail often missed: the 1986 paper rounds the multiplier to 2, while its text also gives 1.96. The 1999 paper uses 1.96 [2,3]. Both are fine; say which you used.
The method assumes the differences are roughly normal and that their spread does not change with the size of the measurement. Check both on a histogram and on the plot [1,3]. If the spread widens as values grow, a log transformation (which turns the limits into ratios) is the usual fix.
Worked example: two peak flow meters, 17 subjects
Bland and Altman compared the large Wright peak flow meter with the mini Wright meter in 17 subjects, each measured twice by each meter. Only the first reading by each meter is used for the method comparison; the second readings are kept for the study of repeatability [2]. The table gives those first readings, with the difference and mean for each subject.
| Subject | Wright (L/min) | Mini Wright (L/min) | Difference (Wright − mini) | Mean of the two |
|---|---|---|---|---|
| 1 | 494 | 512 | −18 | 503 |
| 2 | 395 | 430 | −35 | 412.5 |
| 3 | 516 | 520 | −4 | 518 |
| 4 | 434 | 428 | 6 | 431 |
| 5 | 476 | 500 | −24 | 488 |
| 6 | 557 | 600 | −43 | 578.5 |
| 7 | 413 | 364 | 49 | 388.5 |
| 8 | 442 | 380 | 62 | 411 |
| 9 | 650 | 658 | −8 | 654 |
| 10 | 433 | 445 | −12 | 439 |
| 11 | 417 | 432 | −15 | 424.5 |
| 12 | 656 | 626 | 30 | 641 |
| 13 | 267 | 260 | 7 | 263.5 |
| 14 | 478 | 477 | 1 | 477.5 |
| 15 | 178 | 259 | −81 | 218.5 |
| 16 | 423 | 350 | 73 | 386.5 |
| 17 | 427 | 451 | −24 | 439 |
The 17 pairs match the table on Bland’s page, captured on 28 October 2026 [2]. From them: the mean difference is −2.1 L/min, the standard deviation of the differences is 38.8 L/min, and the correlation between the two meters is 0.94 [2].
With the 1.96 multiplier, the limits of agreement are −78.1 to 73.9 L/min. Figure 2 plots every subject, with the bias line, the limits, and shaded 95% confidence bands for each.
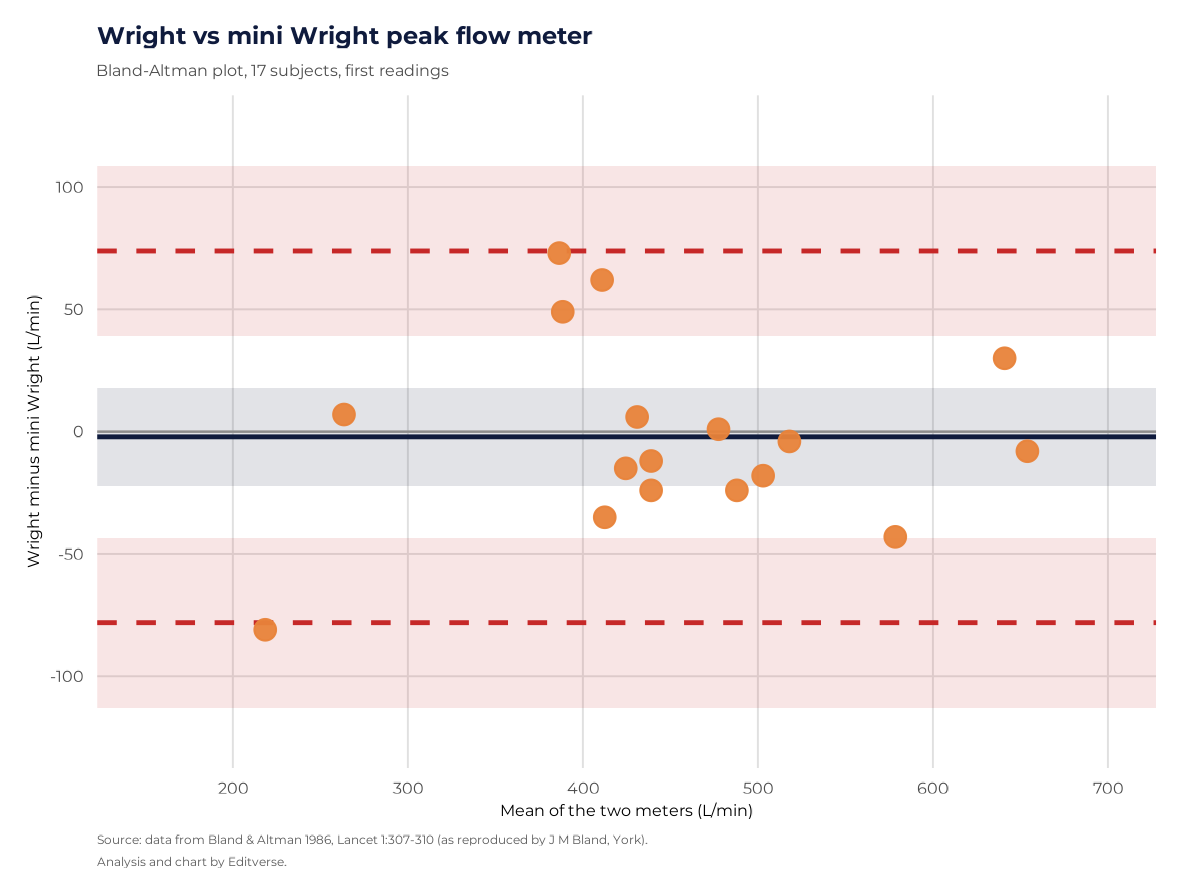
Now check the numbers against what Bland and Altman published (Figure 3). Bias and SD match exactly, and so does the confidence interval for the bias. The limits differ only because the 1986 text used 2 SD, giving −79.7 to 75.5 L/min, while we used 1.96 SD [2].

| Quantity (L/min) | Our calculation | Published by Bland (York page) | Why they differ |
|---|---|---|---|
| Mean difference (bias) | −2.1 | −2.1 | Same |
| SD of differences | 38.8 | 38.8 | Same |
| Limits of agreement | −78.1 to 73.9 (1.96 SD) | −79.7 to 75.5 (2 SD) | Multiplier: 1.96 here, 2 in the 1986 paper |
| 95% CI of the bias | −22.0 to 17.8 | −22.0 to 17.8 | Same |
| 95% CI, lower limit | −112.9 to −43.3 | −114.3 to −45.1 | Different multiplier and standard error formula |
| 95% CI, upper limit | 39.1 to 108.6 | 40.9 to 110.1 | Different multiplier and standard error formula |
Our confidence intervals for the limits use the 1999 standard error formula and 1.96 SD [3]; the published ones use the 1986 approximation and 2 SD [2]. The conclusions are identical.
How to read the result
Bias. The mean difference is −2.1 L/min and its confidence interval, −22.0 to 17.8, includes zero. There is no evidence of a systematic difference between the meters on average [2].
Spread. The limits are about −78 to 74 L/min. Bland and Altman concluded that the mini meter may be 80 L/min below or 76 L/min above the large meter, which would be unacceptable for clinical purposes, and that this lack of agreement is by no means obvious from a plot of one meter against the other [2]. One subject (number 15, Wright 178 and mini 259 L/min, a difference of −81) lies just outside the lower limit, which is about what you expect from a limit that covers 95% of differences.
Precision. With only 17 subjects the confidence intervals are wide: each limit is uncertain by roughly 70 L/min from one end of its interval to the other. Bland and Altman noted that even on the most optimistic interpretation there can be considerable discrepancies between the meters [2]. This is why the sample size matters, a point newer work on agreement studies develops in detail [5,6].
The decision. Whether a spread of about 75 L/min is acceptable is a clinical judgement, not a statistical one. Bland and Altman give a simple illustration: if the meters were unlikely to differ by more than 10 L/min, the large meter could be replaced by the mini meter; if they could differ by 100 L/min, the mini meter would be unlikely to be satisfactory. How far apart measurements can be without causing difficulties is a question of judgement, and it should ideally be defined in advance [2].
The same logic applies in the laboratory. Fang and colleagues compared harmonisation algorithms for immunoassays using 80 patient sera to build the algorithms and 40 to validate them. After their Bland-Altman-based algorithm, the limits of agreement were −23.3% to 23.2%, against −64.6% to 74.6% after the weighted Deming regression approach from ISO 21151:2020 [8]. The Bland-Altman view made the remaining disagreement visible in a way slope and intercept alone did not.
What to report in a paper
Reviews of published studies keep finding the same gaps. Abu-Arafeh and colleagues proposed 13 key reporting features and checked articles from 2013 and 2014 in five anaesthetic journals. They found that the data structure, a plot of the bias and the limits of agreement were almost always reported, but an a priori decision on acceptable limits and an estimate of the precision of the limits were often absent [4]. Gerke later compared seven published reporting proposals, found the same consensus items, and recommended the Abu-Arafeh list for researchers, editors and reviewers [5].
Based on those two reviews, a clear agreement paper reports the following [4,5]:
- the acceptable limits of agreement, decided before the data were collected, with the clinical reason;
- the data structure: how many subjects, how many measurements per subject, and the measurement range;
- the bias with its 95% confidence interval;
- both limits of agreement with their 95% confidence intervals;
- the plot, with differences against the mean of the two methods;
- how you checked normality and whether the spread was constant across the range;
- any transformation used, and the software.
For sample size, Gerke and colleagues summarise recent proposals in an editorial, including the distinction between method comparison and observer variability studies [6]. Earlier rules of thumb were 50 subjects with three replicates on each method, or at least 100 subjects [5].
When another method fits better
Bland-Altman analysis is one of several agreement and reliability tools. The CLSI EP09 guideline for comparing measurement procedures with patient samples describes scatter and difference plots for inspecting the data and Deming and Passing-Bablok regression for characterising bias [9]. For repeated measurements, Taffé extends the work on clinical tolerance limits and probability of agreement; his method needs repeated measurements by at least one of the two methods [7].
| Scenario | Method | What it tells you |
|---|---|---|
| Two continuous methods, one pair per subject | Bland-Altman limits of agreement | Bias and the range of individual disagreement, in measurement units |
| Two methods, several readings per subject | Bland-Altman extensions for replicates, or tolerance limits | Limits that account for within-subject variation |
| You also want to know if the bias changes with the level measured | Deming or Passing-Bablok regression, alongside the difference plot | Constant and proportional bias |
| Ordinal ratings by two raters | Weighted kappa | Agreement between categories |
| Same method repeated | Repeatability and reliability measures such as the intraclass correlation | How consistent one method is with itself |
| Strength of a linear relationship | Pearson or Spearman correlation | Association, not agreement |
For a broader look at when to use correlation or regression, see our guide to regression vs correlation in clinical research.
Free tools for your agreement analysis
These Editverse tools are free and need no signup.
- Bland-Altman Plot Calculator: paste your paired measurements and get the bias, limits of agreement and plot.
- GraphPro: build publication-ready charts, 25 types, with built-in t-test, ANOVA, correlation, and chi-square p-values. Free, no signup.
- StatPro: free statistical calculators and a test-selector tool covering group comparisons, categorical outcomes, time-to-event analysis, and diagnostic accuracy.
- Flowchart Pro: generate PRISMA 2020, PRISMA-ScR, CONSORT, STROBE, STARD, MOOSE, and ARRIVE flow diagrams directly in your browser.
Related Editverse guides
Get your analysis done and written up
If you need the full agreement analysis, assumption checks, tables and a methods paragraph for your manuscript, this is the service built for it.

Need your agreement study checked or analysed? A PhD biostatistician reviews your study design, runs the analysis with assumption checks, and writes the statistical methods paragraph for your manuscript, with revisions included for 60 days.
Limits of agreement FAQ
What are the limits of agreement?
The limits of agreement are the mean difference between two measurement methods plus and minus 1.96 standard deviations of the differences. If the differences are roughly normal, about 95% of future differences between the two methods should fall between them [1,3].
What is the difference between bias and limits of agreement?
Bias is the mean difference, the average amount one method reads above or below the other. The limits of agreement describe the spread around that average, so they show how far apart the two methods can be for an individual patient [1,3].
Why is correlation not enough to show two methods agree?
Correlation measures how closely two sets of values follow a line, not how close they are to each other. In the original peak flow example the correlation was 0.94, yet the two meters could differ by 80 L/min for the same person [1,2].
Should I use 1.96 or 2 standard deviations?
Both appear in the literature. The 1986 paper used 2 standard deviations as a convenient rounding and noted that 1.96 is the more precise multiplier. The 1999 paper uses 1.96 [1,2,3]. State which you used.
What sample size do I need for a Bland-Altman analysis?
There is no single answer. The width of the confidence intervals around the limits depends on the sample size, and in the 17-subject example each limit had a confidence interval about 70 L/min wide. Older rules of thumb suggested 50 subjects with three replicates, or at least 100 subjects, and newer work bases the sample size on the expected interval width [5,6].
Do I have to set the acceptable difference in advance?
Yes, if you want to claim agreement. Bland and Altman said how far apart measurements can be without causing difficulties is a clinical judgement, and that it should ideally be defined in advance [2]. Reviews of published studies find that an a priori limit is often missing [4,5].
What if my differences are not normally distributed or the spread grows with the size of the measurement?
Check a histogram and the plot of differences against means. Common remedies are a log transformation, which gives limits as ratios, or limits based on percentiles of the differences, which need larger samples [1,3,5].
What if I have repeated measurements on each subject?
The standard formula assumes one pair per subject. With replicates use methods built for them: Bland and Altman 1999 set out extensions, and Taffé describes a tolerance-limit approach that needs repeated measurements by at least one method [3,7].
Conclusion
The limits of agreement turn a vague question, do these two methods agree, into a range in the units you measure. Calculate the bias and the limits, give their confidence intervals, plot differences against the mean of the two methods, and compare the result with a clinical threshold that you set in advance. A high correlation cannot do that job, as the original peak flow data show [2]. For help with the analysis, see our statistical analysis and review service.
References
- Bland JM, Altman DG (1986). Statistical methods for assessing agreement between two methods of clinical measurement. Lancet 1(8476):307-310. 10.1016/S0140-6736(86)90837-8
- Bland JM, Altman DG. Statistical methods for assessing agreement between two methods of clinical measurement: the Lancet paper as reproduced on Martin Bland’s page, University of York, including the peak expiratory flow data table (read and captured 28 October 2026). www-users.york.ac.uk/~mb55/meas/ba.htm
- Bland JM, Altman DG (1999). Measuring agreement in method comparison studies. Stat Methods Med Res 8(2):135-160. 10.1177/096228029900800204
- Abu-Arafeh A, Jordan H, Drummond G (2016). Reporting of method comparison studies: a review of advice, an assessment of current practice, and specific suggestions for future reports. Br J Anaesth 117(5):569-575. 10.1093/bja/aew320
- Gerke O (2020). Reporting standards for a Bland-Altman agreement analysis: a review of methodological reviews. Diagnostics 10(5):334. 10.3390/diagnostics10050334
- Gerke O, Pedersen AK, Debrabant B, Halekoh U, Möller S (2022). Sample size determination in method comparison and observer variability studies. J Clin Monit Comput 36(5):1241-1243. 10.1007/s10877-022-00853-x
- Taffé P (2023). Use of clinical tolerance limits for assessing agreement. Stat Methods Med Res 32(1):195-206. 10.1177/09622802221137743
- Fang H, Yang R, Guo J, et al. (2024). Using Bland-Altman plot-based harmonization algorithm to optimize the harmonization for immunoassays. Clin Chem Lab Med 62(11):2205-2214. 10.1515/cclm-2024-0187
- Clinical and Laboratory Standards Institute. EP09: Measurement Procedure Comparison and Bias Estimation Using Patient Samples, 3rd edition (2018). Product page read 28 October 2026. clsi.org/shop/standards/ep09